






The beginner's guide to the FDA De Novo classification process
This article is an excerpt from The beginner's guide to the FDA De Novo classification process ebook.
Contents
- Introduction
- Chapter 1: What is an FDA De Novo request?
- Chapter 2: Contents of a De Novo request
- Chapter 3: Submitting a De Novo request
- Appendix A: Acceptance review checklist
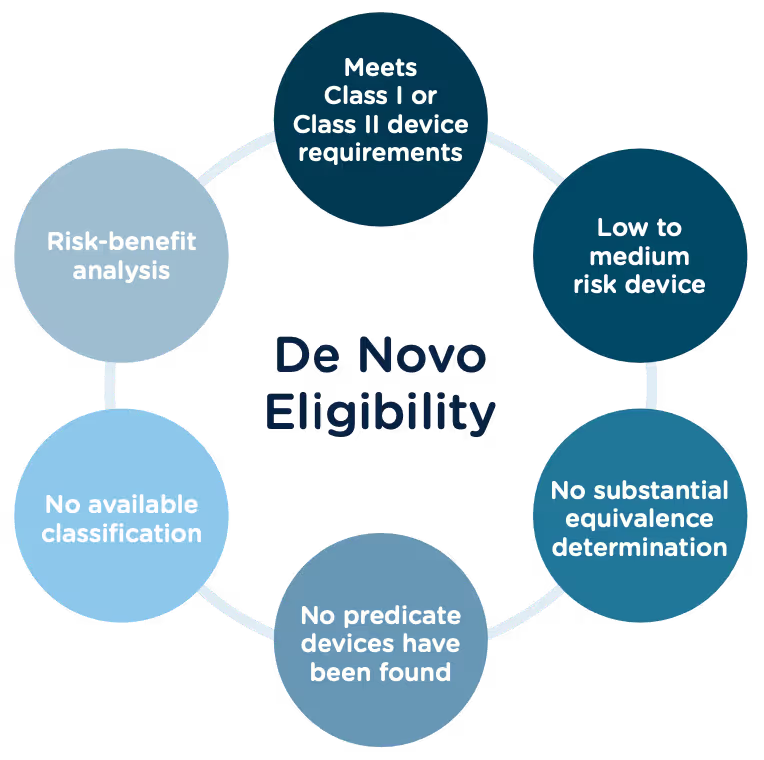
Congratulations, you have successfully developed a new medical device! Now you need to take it to market. Normally in the United States this would mean completing a 510(k) submission. However, the 510(k) relies on “substantial equivalence”—a comparison to a similar device already on the market (also called a predicate device) to assess the risk profile of the new device. What if your device is totally new, and there isn’t a similar device to compare it to? Enter the FDA De Novo process. The De Novo process provides a pathway to market for novel devices with a low to medium risk profile.
What does De Novo mean?
According to the Merriman-Webster dictionary, de novo is a Latin word meaning “as if for the first time; or anew.” Perfectly fitting that the FDA uses this term “De Novo” to describe market approval requests for new medical devices or technology where there is no comparable predicate device on the market.
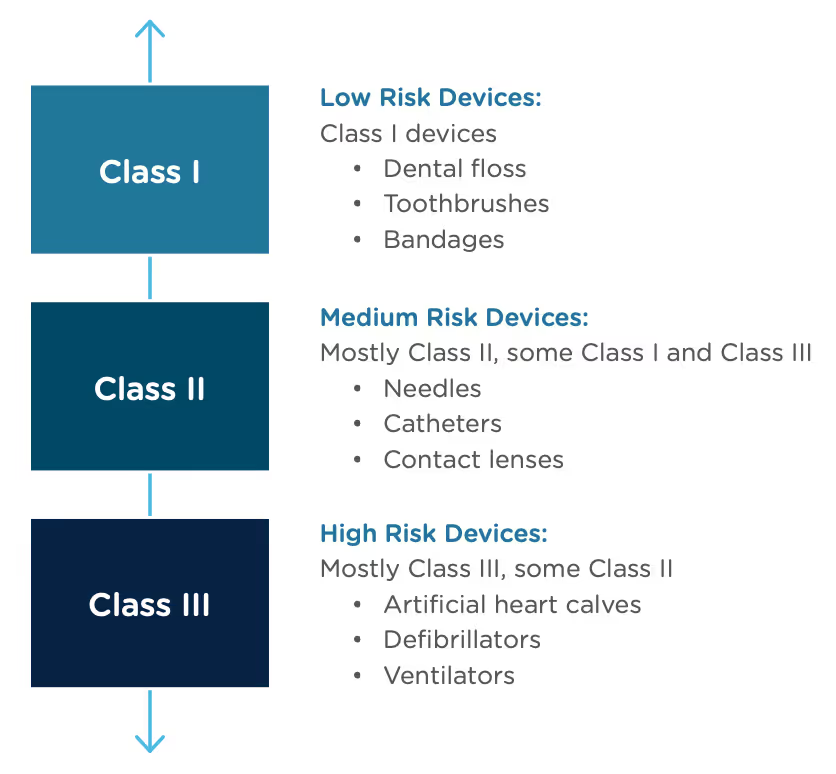
The Food and Drug Administration Modernization Act of 1996 provided the FDA with the authority to create the De Novo Classification Process. It's a process that uses a risk-based strategy for a new, novel kind of medical device, in vitro diagnostic, or medical software solution whose type has previously not been identified and/or classified. It’s a process by which a novel medical device can be classified as a Class I or Class II device, instead of being automatically classified as Class III, which may not be appropriate. Before the implementation of the De Novo process in 1997, all the “not substantially equivalent” (NSE) products were required to be initially classified as a Class III device. But for a lot of devices, this risk class didn’t really make sense. The De Novo process provides a pathway for more accurate classifications of novel, lower-risk devices.
October, 2021, the FDA released a final guidance document "De Novo Classification Process (Evaluation of Automatic Class III Designation)" to provide guidance to the requester (also known as the manufacturer) and the FDA on the process for the submission and review of a De Novo Classification Request under section 513(f)(2) of the Federal Food, Drug, and Cosmetic Act (the FD&C Act). This process provides a pathway to an initial Class I or Class II risk classification for medical devices for which general controls or general and special controls, provide a reasonable assurance of safety and effectiveness, but for which there is no legally marketed predicate device. This guidance document replaced the "New Section 513(f)(2) – Evaluation of Automatic Class III Designation, Guidance for Industry and CDRH Staff" document, dated February 19, 1998.
Consistent with the final rule, the FDA updated the guidance documents below to provide recommendations for submitting De Novo requests, as well as criteria and procedures for accepting, withdrawing, reviewing, and making decisions on De Novo requests, effective January 3, 2022.
- User Fees and Refunds for De Novo Classification Requests
- FDA and Industry Actions on De Novo Classification Requests: Effect on FDA Review clock and Goals
- Acceptance Review for De Novo Classification Requests
The 510(k) and the De Novo processes are similar in that they are both pathways to market for medical devices with low to moderate risk, which is Class I and Class II. The biggest difference between the two is that the 510(k) heavily relies on the concept of "substantial equivalence" to an existing medical device. You must prove this to get the clearance of your 510(k) submission. In the De Novo process, there isn’t a product currently on the market that is “substantially equivalent” to yours, so it’s like starting with a clean slate. For more on the 510(k) process, see our Beginner’s Guide to the 510(k) ebook.
A result of the De Novo process to be aware of is that a successful submission will lead to a new predicate device type that someone else can reference to bring their product to market through the 510(k) process. You’ve done all the work, so now it’s available for anyone to use to provide "substantial equivalence".
De Novo history/timeline
Preparing a De Novo request
1. Do your research! Be sure to complete all the necessary research prior to your submission. You want to be sure that your device is not substantially equivalent to an existing device. Resources to review include:
- The Center for Devices and Radiological Health (CDRH)
- U.S. FDA Device Classification Database
- Device Classification Under Section 513(f)(2)(De Novo)
2. A De Novo request can be submitted with or without a preceding 510(k). There are two options for when you can submit a De Novo request:
Option A: After receiving a not substantially equivalent (NSE) determination (that is, no predicate, new intended use, or different technological characteristics that raise different questions of safety and effectiveness) in response to a 510(k) submission.
Option B: If you’ve determined, after extensive research, that there is no legally marketed device on which to base a determination of substantial equivalence.
3. Be sure all fees are paid to the FDA in advance of submitting a De Novo request. The FDA’s fiscal year begins in October and runs through the following September. Fees have increased each year since they were introduced, but the FDA’s percentage of reviews completed within the 150-day window has increased as well.
A business that is qualified and certified as a “small business” is eligible for a substantial reduction in most of the FDA user fees, including De Novo. The CDRH is responsible for the Small Business Program that determines whether a business is qualified.
Medical Device User Fee Amendments (MDUFA) guidance documents can provide more detailed information about all FDA user fees.
4. The initial request process serves only to determine if the De Novo request is administratively acceptable based upon the Acceptance Checklist. The initial acceptance is followed by substantive review which will determine the final risk classification of your device.
5. A Pre-Submission (Pre-Sub) is a formal written request for feedback from the FDA that is provided in formal written form, and then followed by a meeting. Although a Pre-Sub is not required prior to a De Novo request, it can be extremely helpful to receive early feedback, especially for devices that have not previously been reviewed under a 510(k). If you think you would like to submit a pre-sub first, there are suggested guidelines for submission you should consider:
- Describe your rationale for a Class I or Class II classification for your device.
- Provide the search results of FDA public databases and other resources used to determine that no legally marketed device and no classification for the same device type exists.
- Provide a list of regulations and/or product codes that may be relevant.
- Provide a rationale for why the subject device does not fit within and/or is different from any identified classification regulations, based on available information.
- Identify each health risk associated with the device and the reason for each risk.
- Briefly describe any ongoing and/or planned protocols/studies that need to be completed in order to collect the necessary data to establish the device’s risk profile.
- Provide information regarding the safety and effectiveness of the device. Cite the types of valid scientific evidence you anticipate providing in your De Novo request, including types of data/studies relating to the device’s safety and effectiveness.
- Briefly describe any ongoing and/or planned protocols/studies that need to be completed to collect the necessary safety and effectiveness data.
- Provide protocols for non-clinical and clinical studies (if applicable), including how they will address the risks you anticipate and targeted performance levels that will demonstrate that general controls or general and special controls are sufficient to provide reasonable assurance of safety and effectiveness.
- Share any proposed mitigation measure(s)/control(s) for each risk, based on the best available information at the time of the submission. Highlight which mitigations are general controls and which are special controls and provide details on each.
- Include any other risks that may be applicable, in addition to those identified in the Pre-Sub, given the indications for use for the device.
- If applicable, provide any controls that should be considered to provide a reasonable assurance of safety and effectiveness for the device.
- Provide any non-clinical study protocols that are sufficient to allow the collection of data from which conclusions about device safety and/or effectiveness can be drawn. These protocols should address whether the identified level of concern is the appropriate level of concern for the device software, and if any additional biocompatibility and/or sterility testing is required.
- If clinical data is needed, provide information to show that the proposed study design and selected control groups are appropriate?
6. The FDA will attempt to review the De Novo request submission within 15 calendar days of receipt of the request to make a determination that the submission is declined or accepted for review. If they are unable to complete the review within the 15 days, your submission will automatically move to “accepted for review” status. https://www.fda.gov/regulatory-information/search-fda-guidance-documents/de-novo-classification-process-evaluation-automatic-class-iii-designation
7. There are times when the FDA will refund your application fee. They have created a guidance document “User Fees and Refunds for De Novo Classification Requests” for the purpose of identifying:
- the types of De Novo requests subject to user fees
- exceptions to user fees
- the actions that may result in refunds of user fees that have been paid
When is a De Novo request subject to a user fee?
When will the FDA refund a De Novo user fee?
What fee must be paid for a new device submission following a De Novo “decline” determination?
To continue reading this eBook including a detailed walk-through of all the Traditional 510(k) components, submission requirements and timelines, and an overview of the other 510(k) forms including the Abbreviated 510(k) and the Special 510(k), please register to download the full version.



IMDRF: International Medical Device Regulatory Forum
The medical device industry is vast and diverse, with each country or regional authority having its own regulatory body and requirements. For instance, medical devices are classified in ascending order in the United States, with Class I devices being the lowest risk class. Devices that pose the highest risk to users or patients and require the most regulatory oversight (pacemakers, defibrillators, etc.) are Class III devices, and devices that pose a moderate risk, such as syringes and catheters, are Class II devices. While this is a logical way to categorize medical devices, not every country uses this model.
Medical device regulations will likely never be universally uniform. Still, there is a concerted effort on behalf of regulatory experts from some of the largest medical device markets in the world to harmonize regulations and regulatory best practices. The International Medical Device Regulatory Forum (IMDRF) is a body of medical device regulatory specialists from around the world working together to standardize regulations and “accelerate international medical device regulatory harmonization and convergence.” While the IMDRF isn’t a regulatory body, its guidelines are often adopted by its member countries and adapted to fit their regulations and initiatives. In this article, we’ll give you an overview of the IMDRF, including its history and how its work impacts the global medical device industry.
The IMDRF’s beginning
The IMDRF was conceived in 2011 when Australia, Brazil, Canada, China, the EU, Japan, the US, and the World Health Organization (WHO) met to discuss the formation of this forum. One of their main goals was to build on and expedite the work of the Global Harmonization Task Force (GHTF), the organization that laid the foundation for the IMDRF.
The idea for the GHTF came from a meeting between representatives from the US, EU, Canada, and Japan in 1992. They met to discuss the possibility of forming a “consultative body” of regulatory specialists with the goal of “harmonizing medical device regulatory practices” worldwide. The GHTF held its first meeting in January 1993, forming study groups to evaluate different aspects of regulatory processes, including each member nation's quality management and Good Manufacturing Practices (GMPs). Today, the IMDRF continues to build on the strong foundation laid by the GHTF.
IMDRF members
As mentioned, the IMDRF works to harmonize medical device regulatory best practices worldwide. This mission requires the cooperation of regulators from many countries, performing in-depth studies and publishing guidelines that shape the global regulatory landscape. There are 11 members and their regulatory authorities that comprise the IMDRF:
- Australia - Therapeutic Goods Administration (TGA)
- Brazil - Brazilian Health Regulatory Agency (ANVISA)
- Canada - Health Canada
- China - National Medical Products Administration (NMPA)
- The European Union - European Commission (EC)
- Japan - Pharmaceutical and Medical Device Agency (PMDA)
- Russia - Russian Ministry of Health
- Singapore - Health Sciences Authority (HSA)
- South Korea - Ministry of Food and Drug Safety (MFDS)
- The United Kingdom - Medicines and Healthcare products Regulatory Agency (MHRA)
- The United States of America - US Food and Drug Administration (FDA)
IMDRF functions
The IMDRF is an international medical device regulatory body that offers guidance rather than implementing binding regulations, i.e., they don’t have the authority to mandate directives. According to the FDA, they “develop internationally agreed upon documents related to a wide variety of topics affecting medical devices.” Its members develop these documents by conducting studies via working groups, which we discuss in the next section.
IMDRF working groups
The IMDRF working groups are like subcommittees that focus on specific regulatory issues pertaining to medical devices. They address new technology, trends, and areas where harmonization of standards and regulations would be most beneficial. Their working groups conduct studies and research with the aim of providing regulatory best practices and universally applicable guidelines. There are currently seven active working groups:
- Adverse Event Terminology
- Artificial Intelligence Medical Devices
- Good Regulatory Review Practices
- Medical Device Cybersecurity Guide
- Personalized Medical Devices (PMD)
- Regulated Product Submission
- Software as a Medical Device (SaMD)
There are various participants in every active working group, and these groups can also include regulatory bodies that aren’t IMDRF members. Through their sharing and collection of data, working groups gain valuable insights that enable them to create guidelines that IMDRF members can relatively and easily implement around their existing medical device regulations. This helps to ensure the safety and efficacy of medical devices while promoting the harmonization of regulatory best practices and standards. These documents serve to accelerate the convergence of medical device regulations around the globe and have produced 69 guidances to date.
The IMDRF might not be a regulatory body or have any binding authority, but they are well respected within the medical device community. Their guidance documents help to shape regulatory standards in the world’s largest medical device markets. Staying abreast of IMDRF developments is a regulatory intelligence best practice (much like having a holistic regulatory information management system that provides structure for the medical device industry). Shameless plug aside, understanding the current undertakings of IMDRF working groups is a great way to better understand what’s going on in the medical device regulatory world and what changes might be coming down the road.
To learn more about the IMDRF, visit their website at imdrf.org.

Ask Rimsys!
At Rimsys, we pride ourselves on delivering tools that empower medical device regulatory affairs professionals to simplify and automate daily workflows, react quickly to changing regulations, and track product registrations around the globe. In order to deliver software that empowers RA teams to exceed regulatory campaign expectations, we not only need to understand current and changing global regulations; but we also work hard to understand what the community is talking about, what issues they are trying to solve, and what they would like to explore in more depth.
So - we are asking for your input!
In order to address the topics that are of most interest to you, we’re launching our “Ask Rimsys” campaign. As part of this initiative, we invite you to submit your medical device regulatory questions to us - and once a week we’ll choose a question to answer either via direct social media response, a blog post, or even a short video response. Preference will be given to the following:
- Questions with interest to the broader regulatory community (we will not be able to provide individual or company-specific consultation).
- Questions which touch on regulatory workflows and best practices.
- Questions dealing with the use of technology in optimizing regulatory activities.
If your question is selected, we’ll send you some Rimsys gifts - typically one of our highly requested “Regulatory Ducks in a Row” t-shirts featuring our too-cool for regulatory problems mascot, Reggie the Regulatory Duck. Look for random giveaways during the week too!
We’ll also be holding periodic “As us Anything” webinars with our regulatory team and other experts. These webinars will most often cover a broad topic, such as UDI, and we will take questions ahead of, and during, the webinars. Check out our events page for a list of upcoming webinars and recordings of past webinars.
As a company built by regulatory professionals, we understand the constant pressure on regulatory affairs professionals to stay on top of the changing regulatory landscape and improve your game. That’s why we’re committed to being a reliable friend and a source of relevant information - as well as a provider of world-class RIM software and services. So, help us focus on the issues most important to you by submitting your regulatory questions on Twitter by using #AskRimsys (and be sure to follow us) or answering our short 3-question survey.
And feel free to respond to any of questions or our responses with any regulatory insights you have as well. We look forward to hearing from you, and remember, #AskRimsys!

Introduction to Notified Bodies
The medical device industry is vast, diverse, and heavily regulated, with different countries and regions having varying regulatory requirements and processes. The European Union (EU) is one of the largest markets in the world for medical devices, and if you intend to put a medical device on the market in the EU, there is a good chance you’ll have to work with a Notified Body.
So, what is a Notified Body? In this brief blog post, we’ll discuss what Notified Bodies are, what they do, and how to work with one.
What is a Notified Body?
Notified Bodies play the role of gatekeepers to the EU market for a majority of medical devices/in vitro diagnostics. Notified Bodies for medical devices are independent organizations appointed by EU member states to assess the conformity of certain products before they are placed on the market. Conformity assessments ensure that products are technically safe, compliant, correctly documented, and manufactured under the correct conditions as outlined by applicable legislation, primarily the EU MDR and IVDR in the case of medical devices.
It’s important to note that not all Notified Bodies have the capability to perform assessments for all types of products. For instance, some Notified Bodies have been designated for MDR, meaning they can perform conformity assessments according to EU MDR 2017/745, Article 35, and others can provide conformity assessments for in vitro diagnostics (IVDs) in accordance with EU IVDR 2017/746, Article 32. It’s essential to make sure you work with the right Notified Body to get your medical device to the EU marketplace.
What types of medical devices require a Notified Body?
Medical devices regulated under the MDR as Class IIa, Class IIb, or Class III devices require that a conformity assessment be performed by an accredited Notified Body before receiving a CE marking and being placed in the market. Some Class I devices also require an assessment by a Notified Body, including devices that are sterilized, have a measuring function, or are reusable surgical instruments. Other Class I devices can be self-assessed by the manufacturer.
In vitro diagnostic (IVD) devices designated as Class B, Class C, or Class D also require a conformity assessment by a Notified Body. Only Class A IVDs can be self-assessed by the manufacturer.
What is the role of Notified Bodies under the EU MDR/IVDR?
All medical devices must have CE marking before they can enter the European market. One of the main roles of Notified Bodies is to provide conformity assessment on medical devices before granting them a CE marking, which is also known as a “European Passport,” as it allows products to move relatively freely throughout the EU.
Notified Bodies provide conformity assessment during both the design and production phases of a product, ensuring that medical device manufacturers live up to the requirements of the MDR/IVDR. They audit manufacturing processes and conditions, quality management systems (QMS), and product specifications to make sure that they conform with EU regulations before being placed on the market. It’s also the role of the Notified Body to make sure the manufacturer has the infrastructure in place to market and provide post-market surveillance in the EU.
Notified Bodies provide conformity assessment in support of the EU MDR/IVDR General Safety and Performance Requirements (GSPR) but ultimately, it’s the manufacturer’s responsibility to ensure all requirements have been fulfilled. This includes choosing the right Notified Body to work with to get their medical device on the EU market.
How do you choose the right Notified Body to work with?
It might surprise you to know that not all Notified Bodies are designated for both MDR and IVDR, meaning that it is critical that you do your due diligence to connect with the right Notified Body for your product. Notified Bodies are designated by the competent authority of EU member states to perform certain types of conformity assessments for certain types of medical devices and manufacturing processes/conditions. This means that the Notified Body you work with is largely dependent on the type and classification of your medical device as well as the type of conformity assessment process you want the Notified Body to perform. A list of accredited Notified Bodies is available in the EU NANDO database, which can be searched and filtered by country, specific legislation, and other technical competencies.
A lot rides on selecting the right Notified Body, so it’s imperative that you find the organization that best fits your company’s needs. Learn what you can about their processes, how they communicate with their clients, and even their submission templates and processes. Choose an organization whose standards and processes align with your company’s goals.
According to Rimsys regulatory expert, Bruce McKean, when it comes to working with a Notified Body, “You can benefit from building a relationship with your Notified Body and collaborating with them on various topics. Although MDR and IVDR have forced more stringent requirements that may hinder a consulting relationship, they’re usually willing to offer a certain level of guidance to help you.”
Choosing and working with an Notified Body is a critical step towards getting your product on the EU market, especially for new medical devices. Be sure to do your research before selecting an Notified Body, and communicate with them throughout the product realization phases to ensure your medical device is in compliance with MDR/IVDR requirements. Working successfully with a Notified Body is the best way to fast-track your medical device into one of the largest markets in the world.
Read more about the general safety and performance requirements (GSPR) that Notified Bodies use as the basis for conformity assessments.

MedWatch: The FDA safety information and adverse event reporting program
What is MedWatch?
What should you do if you encounter a serious side effect from a prescription drug you've taken? Or what if you were using a medical device and it malfunctioned and caused you serious harm? Do you contact the manufacturer, your doctor, or your local government? The quick answer is to contact the FDA, and it’s not as complex as you may think.
In the early 1990s, the FDA knew it needed a reliable way to help physicians, health care workers, and all those who work in the medical field to report adverse events related to pharmaceuticals and medical devices. An adverse event is any undesirable experience associated with the use of a medical product or pharmaceutical drug. They wanted a system that could be used to track these events and give them the insight they needed to review and track the reported issues.
In 1993 the FDA introduced the MedWatch program designed to collect voluntary reports of adverse reactions and quality problems of drugs and medical devices, along with all other FDA-regulated products such as dietary supplements, cosmetics, pet food, toys, tobacco, infant formulas, etc. The Stakeholder Engagement Staff within the office of the FDA commissioner is ultimately responsible for this program. They work closely with all FDA centers and offices across the entire agency and serve as a liaison between stakeholder organizations and the general public. In addition, it is their responsibility to report on medical product safety alerts, recalls, statements, and periodic safety labeling change summaries.
MedWatch is not only for medical professionals to report adverse events, but the public is also encouraged to report adverse events as well. And reporting an event to the FDA may be easier than you may think.
MedWatch Reporting
When the FDA approves a medical drug or product, the agency has determined that the benefits of the product outweigh the risks. But, sometimes there are unforeseen risks that are discovered once a product or drug gets to market and people start using it. For example, a product may be used by a larger and more diverse group of people than was represented in the clinical testing. They may differ in the complexity of their health problems or other medications that they use. Because of these unanticipated events, the FDA encourages people to report problems they feel that they’ve experienced.
To report a voluntary event online, you can use the MedWatch Online Voluntary Reporting Form 3500B, which is located on the FDA’s website. Form 3500B is a consumer-friendly reporting form that contains less technical language than the online FDA Form 3500, which is to be used by healthcare professionals. The form will step you through the process and should take about 15-20 minutes to complete. You can submit your contact information (in case they have questions or need clarification) or you can request that your information be kept confidential.
What happens after a report is made to MedWatch?
- FDA staff enter the report into a database so that it is available for review and comparison to other reports.
- An FDA safety evaluator, often a pharmacist, doctor, or nurse, reviews the report and examines the database for similar reports.
- The FDA monitors the data for trends and investigates, if appropriate.
- The FDA takes necessary action to protect public health.
Examples of FDA actions that could result from a report include:
- issuing safety alerts with recommendations to monitor a product's use, adjust the way it is used, or stop using it
- updating the product labeling to reflect new warnings
- inspecting the manufacturer
- requesting a change in the product’s design, manufacturing process, packaging, or distribution
- requesting that a company recall a product
MedWatch is a safety tool for everyone to use. Every MedWatch report is important and is recorded in an FDA database for review and comparison to similar previous reports. Taken together, these reports can identify trends and signal safety problems, leading to an FDA action to protect the public. Remember, reporting can help you, a family member, or someone else avoid harm, serious illness, or even death.
For more information, refer to the FAQ’s on the FDA website.
Join the MedWatch e-mail list here

An overview of 21 CFR Part 820
What is 21 CFR Part 820?
21 CFR 820 is the FDA federal regulation that pertains to quality systems for medical device manufacturers, and it is part of the agency’s set of Current Good Manufacturing Practices (CGMP) for industry. Also referred to as the FDA’s quality system regulation (QSR), the regulation defines design controls and quality processes at all stages of device development in order to ensure that all medical devices marketed in the United States are safe and effective.
21 CFR 820 consists of 15 subparts, which define quality system requirements for each stage and function within the medical device manufacturing process. We define each subpart below.
Federal regulations are organized as Title → Chapter → Subchapter → Part, which means that 21 CFR 820 is short-hand for:

21 CFR 820 vs ISO 13485
ISO 13485 is the de facto international quality system standard for medical device manufacturers, but this is not currently the standard in the United States. While Part 820 and ISO 13485 are structured differently, they have no conflicting requirements. Therefore, companies that are marketing medical devices in the U.S. and in other markets will need to comply with both ISO 13485 and the FDA’s QSR, as defined in 21 CFR 820.
However, the FDA is moving towards harmonizing these standards, and on February 23, 2022 issued a proposed rule to amend the QSR to align more closely with the international consensus standard for Quality Management Systems, primarily by incorporating reference to the ISO 13485 standard. The FDA has published FAQ’s about the proposed rule.
21 CFR Part 820 Requirements
Part 820: General Controls (subpart A)
The General Controls subpart contains three sections providing general information about the regulation, including the scope and applicability along with key definitions.
Scope
The regulation defines current good manufacturing practice (CGMP) requirements governing the methods, facilities, and controls used for the “design, manufacture, packaging, labeling, storage, installation, and servicing of all finished devices intended for human use." Specifically, this subpart defines:
- Applicability:
The requirements of this regulation are intended to ensure the safety and efficacy of all finished medical devices intended for human use that are manufactured in or imported into the United States. Manufacturers that are involved in some, but not all, manufacturing operations should comply with those requirements that are applicable to the functions they are performing.
Exceptions:
- This regulation does not apply to manufacturers of medical device components, but such manufacturers are encouraged to use this regulation as guidance.
- Class I medical devices are exempt from the Design Controls defined in this regulation, except for those listed in § 820.30(a)(2).
- Manufacturers of blood and blood components are not subject to this regulation but are subject to Biologics good manufacturing practices as defined in Subchapter F, Part 606 of the regulation.
Definitions
This section of the regulation contains definitions for a number of terms used throughout the document. The following are the major definitions related to quality records:
- Design history file (DHF): A compilation of records that describes the design history of a finished device.
- Design input: The physical and performance requirements of a device that are used as a basis for device design.
- Design output: The results of a design effort at each design phase and at the end of the total design effort. The finished design output is the basis for the device master record. The total finished design output consists of the device, its packaging and labeling, and the device master record.
- Device history record (DHR): A compilation of records containing the production history of a finished device.
- Device master record (DMR): A compilation of records containing the procedures and specifications for a finished device.
Quality System
The section of the regulation sets the basic requirement for a quality system by stating that “Each manufacturer shall establish and maintain a quality system that is appropriate for the specific medical device(s) designed or manufactured, and that meets the requirements of this part.”
The term “appropriate” is used throughout this regulation and can be open to interpretation. A manufacturer, however, should assume that all requirements are appropriate and applicable except in cases where non-implementation of the requirement can be shown to have no effect on the product's specified requirements or ability to carry out necessary corrective actions.
Quality system requirements (subpart B)
This section of the regulation defines the overall responsibilities and the resources required for the management of the quality system.
Management responsibilities
Executive management is responsible for establishing a quality policy and ensuring adequate resources to effectively maintain and manage the quality system. In addition, management is responsible for establishing a specific quality plan, consisting of relevant practices, resources, activities, and procedures.
Quality audit
Periodic audits of the quality system are required to be conducted by personnel not directly responsible for the activities being audited. The dates and results of each audit need to be documented, along with the results of the audit. It is expected that corrective actions and, when necessary, reaudits, be performed for any identified noncompliances.
Personnel
Manufacturers are responsible for assigning sufficient personnel with appropriate experience and training to perform all tasks required by the quality system plan.
Design controls (subpart C)
Manufacturers of all class II and class III medical devices, along with the specific class I devices listed in paragraph (a)(2) of this regulation, are required to establish design control procedures that ensure design requirements are met as specified.
Design controls shall define:
- Design and development planning - Plans that describe the design and development activities, and responsibilities for these activities and their implementation.
- Design input - Procedures that ensure design requirements are appropriate and address the intended use of the device.
- Design output - Procedures that document design output, including acceptance criteria, so that conformance to design input requirements can be adequately evaluated.
- Design review - Formal and documented reviews of the ensign results that include participation from representatives of all.
- Design verification - Procedures for verifying the device design that confirm that the design output meets the design input requirements.
- Design validation - Procedures for validating the device design, ensuring that devices conform to defined user needs and intended uses, and including testing of production units under actual or simulated conditions.
- Design transfer - Procedures to ensure that the device design is correctly translated into production specification.
- Design changes - Procedures for identifying, documenting, validating, and managing the verification and approval process of all design changes before they are implemented.
- Design history file - A design history file (DHF) is required for each type of device and should include or reference the records necessary to demonstrate that the design was developed in accordance with the approved design plan and device requirements.
Document controls (subpart D)
Medical device manufacturers are required to put in place document controls for all documents required in this regulation.
Document approval and distribution
One or more people must be assigned to review and approve documents prior to issuance. The approval must be documented, include a date and the signature of the approver, and be made available at all locations where applicable. Procedures must also be in place to ensure that obsolete documents are removed and/or prevented from being used.
Document changes
Similar to document approval procedures, changes to documents must be approved, reviewed, and documented. Records of all changes must be maintained.
Purchasing controls (subpart E)
To continue reading this Regulatory Brief, including a definition of the remaining subparts and a comparison of 21 CFR 820 to ISO 13485, please download the full brief.

What is the FDA eSTAR program?
History
In September of 2018, the FDA took their first step in their commitment to improve the process of a 510(k) electronic submission. This commitment was established as part of the Food and Drug Administration Safety and Innovation Act (FDASIA) that was enacted on July 9, 2012, amending the FD&C Act by adding section 745A.
Based on the FDA’s experience with the original eSubmitter process, the Center for Biologics Evaluation and Research (CBER) group piloted a slightly different program and called it the Electronic Submission Template and Resource Pilot Program, thus creating eSTAR. This second attempt at electronic submissions consists of a collection of questions, text, and prompts within a PDF template that guides a user to a ‘complete’ 510(k) electronic submission.
The FDA’s goal of this process is to enhance the quality of submissions by helping to ensure consistent, quality, comprehensive data for the Center for Disease and Radiological Health (CDRH) premarket review. With a standardized format in place, submitters of a 510(k) or De Novo can ensure that their submissions are complete and premarket reviews will be more efficient.
eSTAR timeline

eSTAR Requirements
Currently, eSTAR is a voluntary process that will become mandatory starting October 1, 2023. It is free to use by medical device applicants wishing to submit a 510(k) or a De Novo to the CDRH, but is not to be used for combination products. Although it’s currently free to use, the standard submission fees for 510(k) and De Novo still apply.
A Refuse to Accept (RTA) review (a preliminary review used to ensure the submission is complete) will not be conducted on submitted eSTAR templates as the eSTAR template replaces this checklist and will state if the template is complete or incomplete on the first page. If the eSTAR does not have a completed status, it will not be reviewed by the FDA.
Guidance Information
The FDA has provided final guidance documentation in “Providing Regulatory Submissions for Medical Devices in Electronic Format — Submissions Under Section 745A(b) of the Federal Food, Drug, and Cosmetic Act” (referred to as the “745A(b) device parent guidance”). This guidance document provides a process for the development of templates to facilitate the preparation, submission, and review of regulatory submissions for medical devices solely in electronic format.
The FDA then provided final guidance in “Electronic Submission Template for Medical Device 510(k) Submissions.” There are exemptions listed in the guidance document that may allow users in certain situations to be exempted from eSTAR.
eSTAR Templates
The two templates provided by the FDA are PDF forms that can be filled out and saved, with attachments. The image below shows the device description page of the non-IVDR form. When using the form, red bars will appear in front of any required questions that have not yet been answered. Bars will turn green when all associated questions in a section have been completed. Gray bars indicate an optional question.
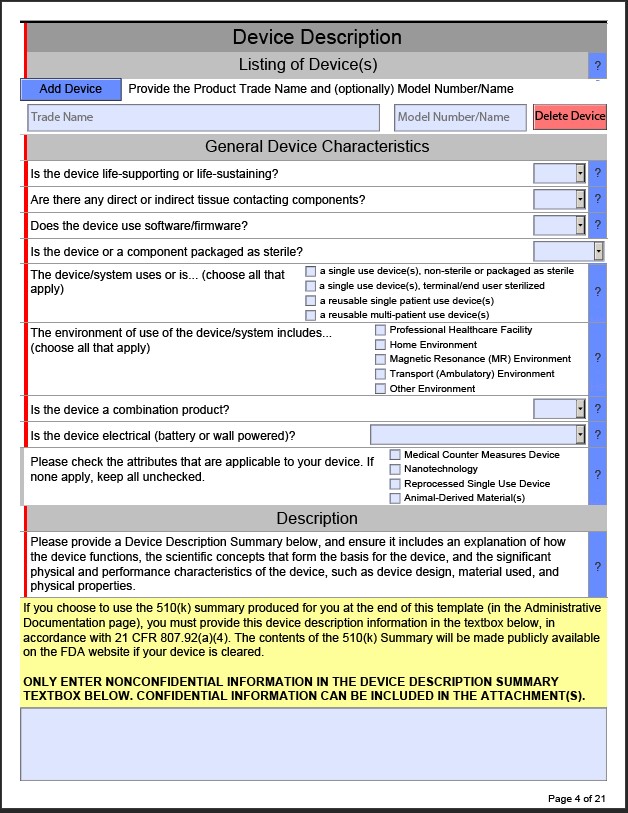
As questions are answered, additional dropdowns may appear that can require users to add additional information. For example, in the Pre-Submission Correspondence and Previous Regulatory Interaction Section within the non-IVD template, if you Select “Yes” the PDF will then add a section where you will need to add the Submission, Submission Number, and copies of the correspondence.
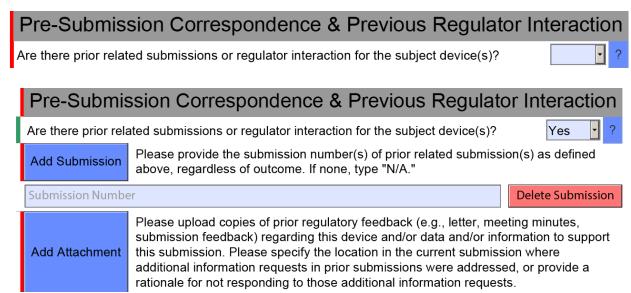
Pop-ups with useful information may also appear. For example, within the non-IVD template, in the General Device Characteristics Section, if a user selects that a device is a single use device, non-sterile or packaged as sterile, a Java Script window will appear with FDA guidance.

A note on embedded attachments: Any embedded attachments may only be used once per eSTAR PDF. You may need to “break up” documentation to fit the eSTAR template requirements if your testing reports cover multiple tests in one document.
What’s involved in a submission?
There are currently two processes for submission:
- The Customer Collaboration Portal
- Mailing the eCopy (CD, DVD or USB drive) containing the eSTAR PDF
First, effective July, 2022, The Customer Collaboration Portal was made available to existing users of the portal if they are the official correspondent of an organization and have also received the FDA email letting them know that they’re eligible.
The second method consists of a printed cover letter with an accompanying eCopy (CD, DVD or USB drive) containing the eSTAR PDF. Note that if the PDF submission exceeds 1 GB in size, it could delay the process, so high-resolution videos and images should only be included when necessary.
- Download the specific eSTAR PDF template for an In Vitro or Non-In Vitro device (see "Current eSTAR versions" section on this linked page).
- Fill out the template accordingly but note that it is only used for constructing - not submitting - your submission.
- The eSTAR does not need to comply with the FDA’s eCopy Guidance document, however, any additional files that are provided with the eSTAR PDF submission will need to comply with it. The FDA strongly recommends not providing additional files with the eSTAR PDF, though, as you already will be embedding your documents within the eSTAR template itself.
- You do not need to provide an Indications for Use page, the Premarket Review Submission Cover Sheet, or a Declaration of Conformity (if applicable) with your submission since they are already built into the eSTAR PDF. An additional option is to also build the 510(k) summary within the template itself instead of writing one.
An eSTAR submission will contain a larger number of files (as they will be embedded in the PDF eSTAR template) than traditional submissions, which are usually combined into one PDF file. We recommend preparing your entire submission before filling out the eSTAR template to minimize the need for reworking the submission.
A note on 510(k) product change submissions: The eSTAR template requires that all subsections be completed, so if you are submitting a 510(k) to address a product change, you will want to include a justification for not including original information in required sections that did not change. Otherwise, all submitted information will be reviewed again, even if it does not differ from the original submission.
Review Timeline
The review timeline will be similar to the review timeline for a non-electronic submission for a 510(k). The guidance document “The 501(k) Program: Evaluating Substantial Equivalence in Premarket Notification [510(k)]” can offer more details. The same would apply for the De Novo in that you would need to reference the guidance document “De Novo Classification Process (Evaluation of Automatic Class III Designation)” for review timelines.
Tracking the Submission
The FDA secures the information about each submission’s progress so only its Official Correspondent (your company’s submission representative) can view it. You will be able to track the progress of your submission by using the Customer Collaboration Portal (CCP).
- If this is your Official Correspondent’s first time tracking a submission online, the FDA will automatically email a link to create a login password soon after the FDA starts its review.
- The FDA currently displays progress online for Traditional, Abbreviated, and Special 510(k) submissions.
- The FDA will formally notify you of your submission’s status by emailing your Official Correspondent with official actions and requests.
The future of eSTAR
These efforts are part of the FDA’s ongoing commitment to work with the industry and to improve the efficiency of the medical device review process. The final guidance for the 510(k) eSTAR was published this month and will become effective October 1, 2023, for 510(k) and De Novo submissions. In the long term if MUDUFA V is passed with the current requests from the FDA, the process will become a required standard for additional submission types such a PMA and will replace the need to mail eCopies containing eSTAR files through the FDA Collaboration Portal.
