








Software as a medical device (SAMD) - classification overview
What is software as a medical device (SaMD)?
As the pace of technological innovation continues to increase, the definition of what constitutes a medical device also continues to evolve as countries update regulations. In 2013, the International Medical Device Regulators Forum (IMDRF) created the Software as a Medical Device working group. Currently chaired by the U.S. FDA, the working group is chartered with developing guidance that encourages innovation while assuring safe and effective products. While SaMD is regulated differently in different countries, this article will focus on the many similarities, and some differences, between the FDA regulations in the U.S. and the MDR regulations in the EU.
In general, medical device software falls into 3 different categories:
- Software as a Medical Device (SaMD): The IMDRF defines SaMD as “software intended to be used for one or more medical purposes that perform these purposes without being part of a hardware medical device.” We list specific examples below, but typically the software classified as SaMD isdesigned to run on generally available hardware, such as Windows computers or mobile devices, or online in the “cloud”. While they may be utilizing data from another medical device, SaMD performs its function independently of any medical equipment or hardware.
- Software in a Medical Device: Sometimes referred to as SiMD, Software in a medical device cannot operate separately from its device, or perform its primary function without the device. For example, the software used to program and run an MRI machine would be useless without the MRI machine. Software in this category is regulated together, and as part of, the whole device.
- Software as an Accessory to a Medical Device: Similarly to Software in a Medical Device, software in this category cannot fulfill a medical purpose on their own. In some cases, a manufacturer may be able to bundle or embed the software in the medical device (making it SiMD) and/or also sell the software separately, making it an accessory.
Similarly, in Europe, the European Commission’s Medical Device Group (MDCG) defines Medical Device Software (MDSW) as a having its own intended purpose. Software which controls a medical device or is otherwise part of a medical device and does not serve a separate medical purpose does not qualify as MDSW, but is regulated by the MDR.
Software in the SaMD category is both a medical device AND software - with relevant regulatory and quality considerations that are specific and unique to each category, yet which must work in tandem. For example, software development best-practices, referenced by the IMDRF SaMD working group, call for iterative feedback loops allowing for quick turnaround of feature requests and bug fixes. While the ability to provide the latest technology and features to the market is an important advantage with SaMD, it does not supersede applicable medical device regulations governing patient safety and efficacy.
Examples of software as a medical device (SaMD)
Because SaMD software, by definition, is capable of running independently of any specific medical device or hardware, there is a relatively clear line between Software as a Medical Device and other medical software:
SaMD regulatory overview and framework
Why does SaMD have independent regulatory considerations?
Over the past decade, the IMDRF, FDA, and other regulatory bodies have worked to better align regulations with the quickly evolving capabilities and nature of digital devices. Software-only devices (SaMD) generate unique opportunities and considerations:
Because SaMD software typically runs on publicly available hardware:
- SaMD software must not only be designed to work on specific platforms (usually multiple), but must also be tested and updated frequently as new hardware and operating systems become available.
- Agile software development methodologies can provide an environment in which fast product feedback loops are supported within the required regulatory framework.
Because SaMD software can be made readily available to the general public, or specific patient groups, using their own devices:
- SaMD software can generate faster user/patient feedback - both for medical professionals and for the device manufacturer. Given this environment, regulatory bodies generally want to enable the market to safely take advantage of new innovations as quickly as possible.
- Product testing needs to take into account the unique and varied environments in which the software may be used, potentially in environments the product is not intended for. The software developer cannot control updates to operating systems or internet browsers, other software that may be running on a user’s device, or the ability for the user to potentially share software or data with others.
- The advantages of quickly delivering product fixes and updates need to be measured against potentially introducing new, possibly misunderstood or unwanted features, to all users at once.
SaMD and MDSW risk-based categories
As with all medical devices, the FDA and European MDR classify SaMD and MDSW, respectively, based on the potential impact to patient or public health. The SaMD categorization framework from the IMDRF is an effort “to introduce a foundational approach, harmonized vocabulary, and general and specific considerations, for manufacturers, regulators, and users alike to address the unique challenges associated with the use of SaMD...” This framework provides guidance only for today’s medical software developers, as well as regulatory bodies, such as the FDA. The chart below lists these risk categories by the state of the healthcare situation or condition and by the significance of the information provided by the SAMD:
SaMD categories
SaMD Category I:
SaMD Category I software can provide information for both Serious and Non-Serious health conditions or diseases. Software dealing with serious conditions can be classified in Category I only if it is providing information to inform, not drive, clinical management and is of low impact. Otherwise, Category I SaMD software provides information related to non-serious diseases or health conditions.
Example: Software that collects exercise-related data, such as heart rate, number of steps, and distance walked. If the information is stored and/or transmitted for use by a qualified professional the software is considered to be in Category I, as long as the information is not used by the software to make treatment recommendations directly to the patient or healthcare provider.
SaMD Category II:
SaMD software in Category II may be used to provide information relevant to a non-serious, serious, or critical healthcare condition or disease, depending on the significance of the information it provides to the healthcare decision. Software that is used to treat or diagnose a health condition is only classified in Category II for non-serious health conditions. Software that provides information regarding serious or critical health conditions or diseases will be classified in Category II only if it provides information to drive or inform, respectively, clinical management decisions (as opposed to providing treatment or diagnosis recommendations directly).
Example: SaMD that monitors a diabetic patient’s carbohydrate intake and blood glucose level to calculate recommended insulin dose.
SaMD Category III:
SaMD software that provides information to treat or diagnose serious conditions - or which drives clinical management for a critical condition - is classified in Category III.
Example: SaMD that analyzes individual data from at-risk populations for a specific type of cancer, and is used to develop preventative intervention strategies.
SaMD Category IV:
SaMD Category IV software provides information used to treat or diagnose a critical health condition and is considered to be very high impact.
Example: SaMD that evaluates images of skin lesions in order to determine malignancy.
For SaMD intended to be used in multiple healthcare situations, the software will be categorized at the highest category according to the SaMD definition statement.
SaMD within the FDA and MDR regulatory framework
The graph below relates SaMD categories with FDA medical device classes, and further identifies where an independent review is recommended by the FDA. For additional information see Software as a Medical Device (SaMD): Clinical Evaluation. Guidance for Industry and Food and Drug Administration Staff.
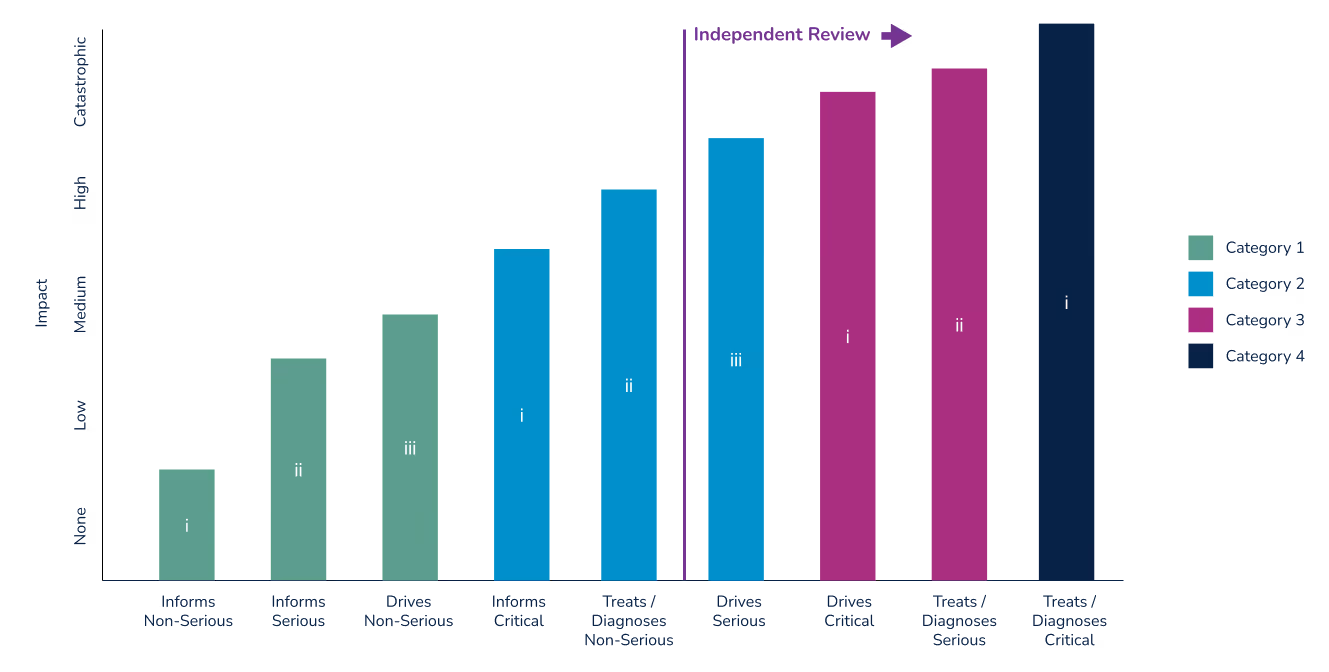
Note that FDA regulatory classifications more closely align with the IMDF’s SaMD categories than do those defined by under the European MDR. In the U.S., a device is classified by identifying similar, predicate devices. The simpler 510(k) pre-market submission can be used if a manufacturer can show that their device is substantially equivalent to a Class I or II device. With few exceptions, devices that are Class III are subject to the more rigorous Pre-Market Authorization (PMA) process. Devices where no substantial equivalent can be shown are subject to to the PMA or De Novo regulatory submissions processes. The De Novo process was implemented in 2010 to provide a pathway for novel devices with lower risk profiles.
Medical Device Software is classified by the European Commission’s Medical Device Coordination Group (MDCG) into Class I, II, or III. For devices falling under the IVDR, the MDR defines four classes using letters; A, B, C, and D.
In the EU, a rules-based framework is used to classify devices. MDSW classification is relatively complex, using a series of 22 “waterfalling” rules with yes/no questions that lead to a final classification of each device. While we won’t go into detail in this article on each of the rules, Rule 11 does deserve discussion. (You can read the Guidance on Classification of Software for MDR and IVDR here).
The MDR’s “rule 11” regarding MDSW classification was released in 2017. This rule states, in part, that “Software intended to provide information which is used to take decisions with diagnosis or therapeutic purposes is classified as class IIa.” The rule then provides 2 exceptions that increase the MDSW classification in cases where the decisions could cause “a serious deterioration of a person’s state of health or a surgical intervention” (class IIb), or could cause “death or an irreversible deterioration of a person’s state of health” (class III).
As a result of this rule, very few MDSW products can be classified as Class I, meaning that the majority of MDSW is subject to conformity assessments by a Notified Body. Medical software manufacturers marketing their product in Europe should therefore not rely on previous product classifications as a guide.
The future of regulatory approval for software as a medical device (SaMD)
The FDA recently released a new draft guidance document addressing the Content of Premarket Submissions for Device Software Functions. This is a major update of the 2005 guidance on pre-market submissions for software in medical devices and is also long overdue, given the pace of change in the software industry (the FDA originally committed to delivering this update in their fiscal year 2019 as part of the MDUFA IV agreement). This guidance sets out requirements for all pre-market submissions, including 510(k), DeNovo, and PMA submissions.
The recent draft document provides additional guidance around the documentation required for premarket submissions. It defines an “enhanced” level of documentation required for software that is a Class III device, combination product, Blood Establishment Computer software, or when the failure of the software would present probable risk of death or serious injury.
Staying on top of medical device classifications
Classifying a medical device and gaining regulatory clearance can be a complex process, especially if the device contains software or other emerging technology where some regulatory bodies may be further along than others in developing applicable regulations. For additional information about some of the common pathways to market for new products in the U.S., read our Beginner’s Guide to the FDA 510(k) and Beginner’s Guide to the FDA De Novo Classification Process.
Interested in learning how Rimsys can automate your submission process? Request a custom demo of our RIM platform.

PSUR: Periodic safety update reports for medical device and in vitro diagnostic products
For many medtech companies, structured, post-market surveillance reporting requirements are a new component of a product’s regulatory lifecycle. The EU MDR/IVDR regulations introduced a host of new post-market surveillance requirements for medical devices and in vitro diagnostics made available for sale in the EU—including regular summary reporting to be recorded within the device technical file or submitted directly to Notified Bodies. This article provides a brief background of Periodic Safety Update Reports (PSUR), the types of products which they’re applicable to, and what content is typically included in a PSUR.
What is a PSUR?
The Periodic Safety Update Report or PSUR is not a new term, at least to the pharmaceutical community. The industry has been operating with regulations related to PSUR for some time. But for the medical device and IVD community, it’s a new requirement that stems from EU Regulations MDR 2017/745 (article 86) and IVDR 2017/746 (article 82). A PSUR is basically a report summarizing critical actions and conclusions derived from post-market surveillance data of a medical or in vitro diagnostic device. All associated preventive and corrective actions should be documented throughout the lifetime of the device, even if the product is no longer on the market.
The introduction of the PSUR under the MDR and IVDR requires a more consistent, standardized, and systematic review of all Post Market Surveillance (PMS) data by medical and IVD device manufacturers. The PSUR is meant to summarize the results and conclusions of the analysis of the post-market surveillance data that has been gathered, resulting from the activities detailed in either the Post-Market Surveillance Plan (PMSP). In addition, any rationale and description of any preventive and corrective actions taken for safety reasons should be included.
The PSUR is for specific classes of medical and IVD devices, as per the table below:
Note: a European competent authority or Notified Body can request your PMSR or PSUR at any given time.
What is the purpose of a PSUR?
The purpose of a PSUR is for manufacturers to demonstrate with objective evidence that they have designed and deployed a Post-Market Surveillance system which uses data to drive action within their Quality Management System and ensure the continued safety, performance, and efficacy of their devices. It’s intended for moderate and high-risk devices (MD Class IIa, IIb, III: IVD Class C and D) and provides a detailed summary of results and conclusions derived from the PMS data.
What’s included in a PSUR?
Medical device and IVD manufacturers need to prepare a PSUR for each device, and where relevant, for each category or group of devices. The manufacturer is responsible for preparing and updating the PSURs and making it part of the technical documentation that should be included with the Essential Principles/GSPR’s. These reports must be clear, organized, searchable and in easy-to-read format.
The PSUR should be a stand-alone document. While the content of a PSUR can vary, depending on the amount of specific data the vendor chooses to include, the PSUR should, at a minimum, always include: an executive summary, safety conclusions and benefit-risk determination, main findings of the Post Market Clinical Follow-up (PMCF) [or Post Market Performance Follow-up for IVDs], vigilance data, information about sales volume, user population, and usage frequency. A PSUR is meant to provide an overview of information, not to be a complete duplicate of all the PMS report information.
Something very important to note, A PSUR is required throughout the lifetime of the device plus the shelf-life where relevant. So for example, A single use device could have a lifetime of 1 year, but a shelf life of 5 years. After the end of device production, the PSUR can be stopped only when the cumulative data of the PSUR issued for this device covers the duration of the shelf life (6 years).
What is the format of a PSUR?
The PSUR format is composed of two elements: the PSUR form and the PSUR report.
The PSUR report is a PDF file that the manufacturer will be required to upload in EUDAMED for class III devices and for implantable devices. The PSUR form is an electronic form that will be completed by the manufacturer in EUDAMED, after they have finished the “completeness” check.
The PSUR form contains all your relevant administrative information as well as data to identify and distinguish between different PSURs for the same device. It should also contain data necessary for the registration of the PSUR in EUDAMED. The PSUR form will be available by the Commission on their website at a later date to be announced.
The PSUR report will contain all of the core content including the executive summary, grouping of devices, sales volume, and PMS data discussed in the previous section.
Keeping on top of technical documentation
PSUR requirements, and PMR data are now a critical part of the technical documentation that regulatory affairs professionals in medtech are required to maintain. Along with the expanded GSPR requirements that come with the MDR/IVDR rollouts, traditional approaches to managing technical docs are no longer effective, and can be prohibitively time-consuming to maintain. Regulatory Intelligence Management (RIM) systems, like Rimsys, can provide a much more powerful, effective, and streamlined way to manage all of a products’ technical files and supporting documentation.
To learn more about RIM systems, read our case study to see how a global leader in in vitro diagnostics was able to reduce the time spent on maintaining technical docs by 99% or request a custom demo of the Rimsys platform.

De Novo classification process: a beginner's guide
This article is an excerpt from The beginner's guide to the FDA De Novo classification process ebook.
Contents
- Introduction
- Chapter 1: What is an FDA De Novo request?
- Chapter 2: Contents of a De Novo request
- Chapter 3: Submitting a De Novo request
- Appendix A: Acceptance review checklist
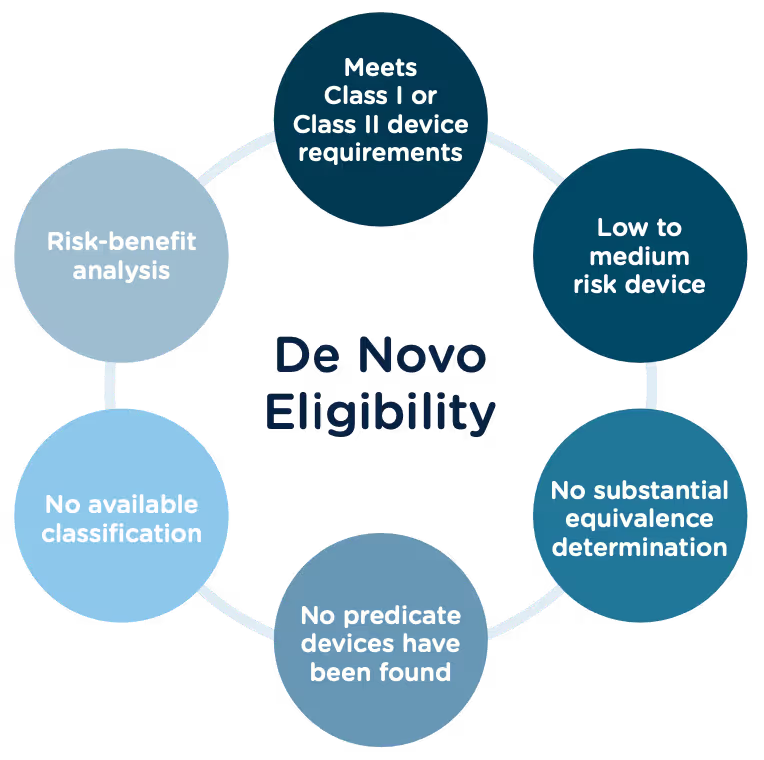
Congratulations, you have successfully developed a new medical device! Now you need to take it to market. Normally in the United States this would mean completing a 510(k) submission. However, the 510(k) relies on “substantial equivalence”—a comparison to a similar device already on the market (also called a predicate device) to assess the risk profile of the new device. What if your device is totally new, and there isn’t a similar device to compare it to? Enter the FDA De Novo process. The De Novo process provides a pathway to market for novel devices with a low to medium risk profile.
What does De Novo mean?
According to the Merriman-Webster dictionary, de novo is a Latin word meaning “as if for the first time; or anew.” Perfectly fitting that the FDA uses this term “De Novo” to describe market approval requests for new medical devices or technology where there is no comparable predicate device on the market.
The Food and Drug Administration Modernization Act of 1996 provided the FDA with the authority to create the De Novo Classification Process. It's a process that uses a risk-based strategy for a new, novel kind of medical device, in vitro diagnostic, or medical software solution whose type has previously not been identified and/or classified. It’s a process by which a novel medical device can be classified as a Class I or Class II device, instead of being automatically classified as Class III, which may not be appropriate. Before the implementation of the De Novo process in 1997, all the “not substantially equivalent” (NSE) products were required to be initially classified as a Class III device. But for a lot of devices, this risk class didn’t really make sense. The De Novo process provides a pathway for more accurate classifications of novel, lower-risk devices.
October, 2021, the FDA released a final guidance document "De Novo Classification Process (Evaluation of Automatic Class III Designation)" to provide guidance to the requester (also known as the manufacturer) and the FDA on the process for the submission and review of a De Novo Classification Request under section 513(f)(2) of the Federal Food, Drug, and Cosmetic Act (the FD&C Act). This process provides a pathway to an initial Class I or Class II risk classification for medical devices for which general controls or general and special controls, provide a reasonable assurance of safety and effectiveness, but for which there is no legally marketed predicate device. This guidance document replaced the "New Section 513(f)(2) – Evaluation of Automatic Class III Designation, Guidance for Industry and CDRH Staff" document, dated February 19, 1998.
Consistent with the final rule, the FDA updated the guidance documents below to provide recommendations for submitting De Novo requests, as well as criteria and procedures for accepting, withdrawing, reviewing, and making decisions on De Novo requests, effective January 3, 2022.
- User Fees and Refunds for De Novo Classification Requests
- FDA and Industry Actions on De Novo Classification Requests: Effect on FDA Review clock and Goals
- Acceptance Review for De Novo Classification Requests
The 510(k) and the De Novo processes are similar in that they are both pathways to market for medical devices with low to moderate risk, which is Class I and Class II. The biggest difference between the two is that the 510(k) heavily relies on the concept of "substantial equivalence" to an existing medical device. You must prove this to get the clearance of your 510(k) submission. In the De Novo process, there isn’t a product currently on the market that is “substantially equivalent” to yours, so it’s like starting with a clean slate. For more on the 510(k) process, see our Beginner’s Guide to the 510(k) ebook.
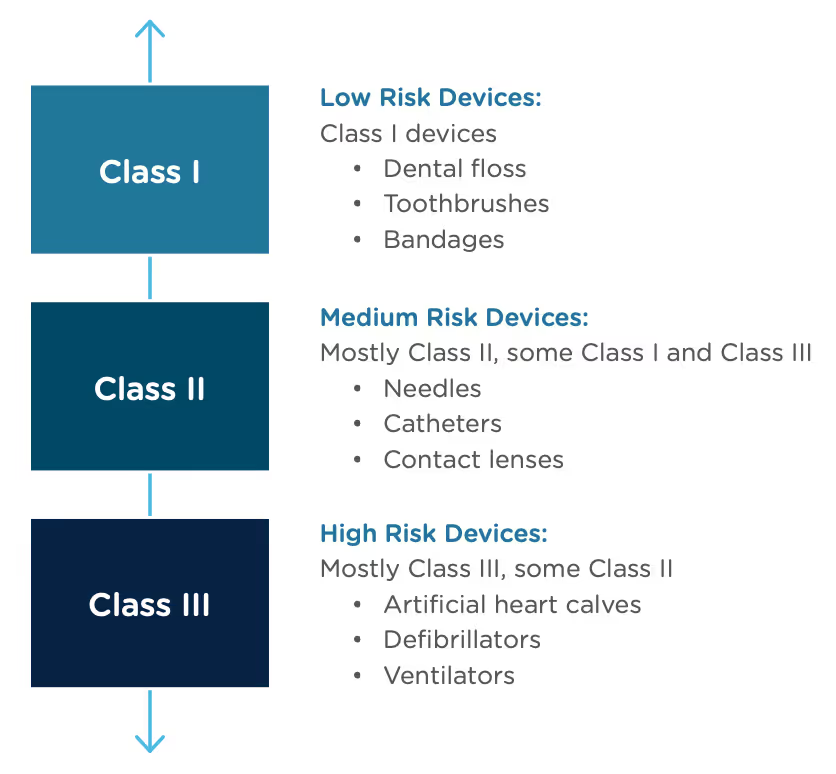
A result of the De Novo process to be aware of is that a successful submission will lead to a new predicate device type that someone else can reference to bring their product to market through the 510(k) process. You’ve done all the work, so now it’s available for anyone to use to provide "substantial equivalence".
De Novo history/timeline
Preparing a De Novo request
1. Do your research! Be sure to complete all the necessary research prior to your submission. You want to be sure that your device is not substantially equivalent to an existing device. Resources to review include:
- The Center for Devices and Radiological Health (CDRH)
- U.S. FDA Device Classification Database
- Device Classification Under Section 513(f)(2)(De Novo)
2. A De Novo request can be submitted with or without a preceding 510(k). There are two options for when you can submit a De Novo request:
Option A: After receiving a not substantially equivalent (NSE) determination (that is, no predicate, new intended use, or different technological characteristics that raise different questions of safety and effectiveness) in response to a 510(k) submission.
Option B: If you’ve determined, after extensive research, that there is no legally marketed device on which to base a determination of substantial equivalence.
3. Be sure all fees are paid to the FDA in advance of submitting a De Novo request. The FDA’s fiscal year begins in October and runs through the following September. Fees have increased each year since they were introduced, but the FDA’s percentage of reviews completed within the 150-day window has increased as well.
A business that is qualified and certified as a “small business” is eligible for a substantial reduction in most of the FDA user fees, including De Novo. The CDRH is responsible for the Small Business Program that determines whether a business is qualified.
Medical Device User Fee Amendments (MDUFA) guidance documents can provide more detailed information about all FDA user fees.
4. The initial request process serves only to determine if the De Novo request is administratively acceptable based upon the Acceptance Checklist. The initial acceptance is followed by substantive review which will determine the final risk classification of your device.
5. A Pre-Submission (Pre-Sub) is a formal written request for feedback from the FDA that is provided in formal written form, and then followed by a meeting. Although a Pre-Sub is not required prior to a De Novo request, it can be extremely helpful to receive early feedback, especially for devices that have not previously been reviewed under a 510(k). If you think you would like to submit a pre-sub first, there are suggested guidelines for submission you should consider:
- Describe your rationale for a Class I or Class II classification for your device.
- Provide the search results of FDA public databases and other resources used to determine that no legally marketed device and no classification for the same device type exists.
- Provide a list of regulations and/or product codes that may be relevant.
- Provide a rationale for why the subject device does not fit within and/or is different from any identified classification regulations, based on available information.
- Identify each health risk associated with the device and the reason for each risk.
- Briefly describe any ongoing and/or planned protocols/studies that need to be completed in order to collect the necessary data to establish the device’s risk profile.
- Provide information regarding the safety and effectiveness of the device. Cite the types of valid scientific evidence you anticipate providing in your De Novo request, including types of data/studies relating to the device’s safety and effectiveness.
- Briefly describe any ongoing and/or planned protocols/studies that need to be completed to collect the necessary safety and effectiveness data.
- Provide protocols for non-clinical and clinical studies (if applicable), including how they will address the risks you anticipate and targeted performance levels that will demonstrate that general controls or general and special controls are sufficient to provide reasonable assurance of safety and effectiveness.
- Share any proposed mitigation measure(s)/control(s) for each risk, based on the best available information at the time of the submission. Highlight which mitigations are general controls and which are special controls and provide details on each.
- Include any other risks that may be applicable, in addition to those identified in the Pre-Sub, given the indications for use for the device.
- If applicable, provide any controls that should be considered to provide a reasonable assurance of safety and effectiveness for the device.
- Provide any non-clinical study protocols that are sufficient to allow the collection of data from which conclusions about device safety and/or effectiveness can be drawn. These protocols should address whether the identified level of concern is the appropriate level of concern for the device software, and if any additional biocompatibility and/or sterility testing is required.
- If clinical data is needed, provide information to show that the proposed study design and selected control groups are appropriate?
6. The FDA will attempt to review the De Novo request submission within 15 calendar days of receipt of the request to make a determination that the submission is declined or accepted for review. If they are unable to complete the review within the 15 days, your submission will automatically move to “accepted for review” status. https://www.fda.gov/regulatory-information/search-fda-guidance-documents/de-novo-classification-process-evaluation-automatic-class-iii-designation
7. There are times when the FDA will refund your application fee. They have created a guidance document “User Fees and Refunds for De Novo Classification Requests” for the purpose of identifying:
- the types of De Novo requests subject to user fees
- exceptions to user fees
- the actions that may result in refunds of user fees that have been paid
When is a De Novo request subject to a user fee?
When will the FDA refund a De Novo user fee?
What fee must be paid for a new device submission following a De Novo “decline” determination?
To continue reading this eBook including a detailed walk-through of all the Traditional 510(k) components, submission requirements and timelines, and an overview of the other 510(k) forms including the Abbreviated 510(k) and the Special 510(k), please register to download the full version.

GUDID: An overview of the FDA's Global Unique Device Identification Database
GUDID is an important source of information as well as a key regulatory requirement for medtech manufacturers who market medical devices, in vitro diagnostics, or medical software in the United States. This article provides an overview of the system, and links to relevant FDA resources you can visit to learn more.
What is GUDID?
GUDID is an acronym for the Global Unique Device Identification Database, a central repository of detailed medical device information created by the FDA. It is often pronounced “Good ID”. The GUDID was implemented as a component of the FDA’s Unique Device Identifier (UDI) requirements, and serves as a digital hub of all the UDI information for all the medical devices that are marketed in the United States.
The GUDID database is designed to help identify and trace all medical devices sold in the U.S., and provides detailed specifications about each device including manufacturer and production information, intended use, safety, and storage and handling requirements. The database is accessible to regulators, manufacturers, healthcare providers, insurers, and the public at large.
GUDID history
The GUDID was implemented as a part of the FDA’s UDI system. This system requires that each medical device have a unique identification code that is included in the device label (printed on the device itself or its packaging) in both machine and human readable format. An example of a UDI code is included below. The UDI code contains information about the device, the manufacturer, and when/where the device was manufactured.
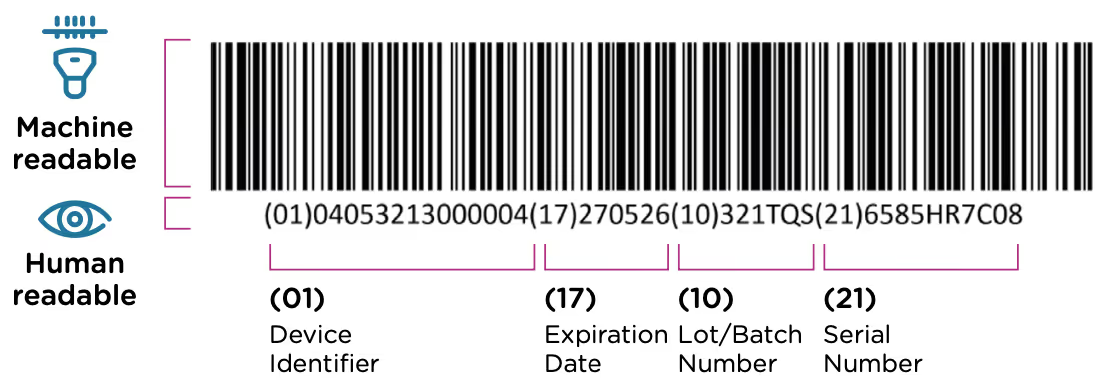
The FDA’s UDI program was established in 2013, when a rule was issued requiring all medical devices to carry a UDI by 2020. The GUDID database was included with the same regulation, and manufacturers were required to submit all of their UDI information electronically to this database as the requirements came online for different device classes. The overall UDI requirements rollout had the following timeline:
The GUDID database was launched ahead of the first device deadline in December, 2013, and the public access portal AccessGUDID went live in May, 2015.
Who should submit data to the GUDID?
The FDA specifies that the GUDID submission is the ultimate responsibility of the “device labeler”. This is the entity/company who is identified on the device’s label (which also contains the UDI code). So the same entity that attaches the UDI to the device, is also responsible for the electronic GUDID submission. In almost all cases this is the manufacturer of the device, however, it can be the U.S. distributor for the product if they are named on the product’s label.
What data must be submitted to the GUDID?
The information submitted to the GUDID includes all of the device information that is in the UDI code along with additional information about product distribution, product and packaging size, sterilization, and storage and handling instructions. The following information is required to be included with each submission:
- Device identifier information - This includes the device identifier (the first part of the UDI code), a detailed device description, and information about the labeler including the DUNS code, and company name and address.
- Commercial distribution - This includes the distribution status—whether or not the device is in commercial distribution, and the distribution end date—when the device will no longer be distributed.
- Alternative identifiers - If the device has another DI, either a direct marketing DI, a distinct packaging DI, one from another issuing agency, or one that was used previously, this information must be provided.
- Customer contact information - A phone and email address for patients or consumers who have questions about the device.
- FDA codes and listing number - If the device completed a pre-market authorization (PMA) that should be included as well.
- Manufacturing information - Manufacturing date, lot or batch number, serial number, and expiration date for the device.
- Latex information - Whether or not the device or its packaging contains rubber components.
- Device dimensions - What is the clinically relevant size and unit of measure for the device.
- Storage and handling - Requirements and parameters for storage including temperature, humidity, and pressure.
- Sterilization - Whether the device is packaged as sterile or requires sterilization prior to use.
The FDA provides a detailed spreadsheet of data requirements that you can use to prepare your submission.
Creating a GUDID submission
In addition to gathering the required information (and obtaining a UDI code for your device) there are several additional steps to complete in order to create a GUDID submission for your product. First, if you don’t have one, you’ll need to create a GUDID account. The FDA allows you to request an account online. Note that you will need to have a DUNS number for your business. If you don’t have one you can request one from Dun & Bradstreet at no cost.
There are two ways that you can enter your submission. You can do this online through the GUDID Web application. The FDA also allows you to submit your GUDID information all at once using an XML file that complies with Health Level 7 (HL7) Structured Product Labeling (SPL) formats. These submissions are made via the FDA Electronic Submissions Gateway, and require you to set up a gateway account.
In addition, some software providers (like Rimsys) include the ability to make electronic GUDID submission directly from their tools. They provide a system to organize and manage UDI data for the US and other countries, and can ensure that GUDID information for your products is kept up to date.
The global proliferation of UDI regulations
The GUDID was one of the first public databases of medical device information, but many additional countries and regions have followed suit. The European Union, China, South Korea, and Taiwan have all introduced UDI databases and requirements that manufacturers submit records for all of their products sold in-market, and ensure that they are kept up to date.
For more information about global UDI programs and timelines, see our UDI quick reference guide. And you can find more detailed information about the specific requirements in the EU and China in our Ultimate guide to the MDR/IVDR UDI and Ultimate Guide to the China NMPA UDI requirements ebooks.

Rimsys raises $16M Series A to bring regulatory order to the medtech industry
We’re excited to announce that we’ve closed $16M in Series A financing led by Bessemer Venture Partners, with participation from Allos Ventures, Private Opportunities, and Innovation Works. Rimsys was created because there wasn’t a viable regulatory information management (RIM) solution on the market for medtech companies, leaving regulatory affairs (RA) teams to manage increasingly complex work with spreadsheets. The growth that we’ve seen (3X this year), and the work we’ve done with some of the world’s largest medtech companies including Johnson & Johnson, Terumo, Siemens, and the Cooper Companies, makes us incredibly excited about what’s to come.
Regulatory digitization and automation for the medtech industry
The regulatory landscape for medical device, in vitro diagnostic, and medical software products is growing increasingly complex. The implementation of the new European Union Medical Device Regulations in May, to be followed by the In Vitro Diagnostic Regulations next year, brought new general safety and performance, unique device identification, and post-market surveillance requirements that manufacturers must comply with. Research from MedTech Europe predicts that as many as 76% of products will be withdrawn from the market as a result.
Growing complexity isn’t limited to the EU region. This year, Australia has released new essential principles requirements, Canada has expanded post-market requirements, and China has launched a new UDI system. The simple fact is that the largely manual way that RA teams have managed processes won’t work moving forward.
The Rimsys RIM Platform provides an automated, digital alternative to these traditional approaches. It’s a 100% cloud-based software solution that’s specifically designed around medtech regulatory activities and processes.
Rimsys provides a centralized "single source of truth" for all regulatory information and documents. It automates regulatory submissions, including product and UDI registrations, and monitors expiration dates, applicable standards, and regulations for changes that might impact products. It’s a single, integrated solution that supports the full breadth of regulatory activities, and organizes all of it at the individual product level, giving medtech companies unprecedented visibility into and control over their regulatory processes.
New leadership to drive continued growth
We’re also excited to announce new company leadership that will help us through our next phase of growth. We’ve added two new executive leaders with extensive industry experience: Adam Price, former head of post-market surveillance at Philips, and Christine Robertson, former IT leader supporting regulatory at Thermo Fisher Scientific. Adam will lead post-market strategy for Rimsys, developing new offerings to streamline and simplify that part of the regulatory lifecycle. Christine will lead implementation and professional services, bringing best-practices from successful large-scale RIM deployments to all of our customers.
We’ve also added two new board members: Andrew Hedin, Partner at Bessemer Ventures, and Eric Boduch, Co-founder of Pendo, a $2.6B SaaS company that helps companies develop better software products. Both bring a wealth of start-up, SaaS, and industry experience that will be incredibly valuable as we scale the company.
What’s next
Our goal is to build a comprehensive software platform for medtech regulatory affairs that supports activities across the regulatory lifecycle from pre-market to market placement to post-market surveillance. This year we became the first vendor to offer UDI management directly integrated with product registration data. And we announced a new partnership with Clarivate to bring world-class regulatory intelligence into the Rimsys platform where customers can leverage it directly within automated processes.
We will continue to expand our capabilities at an even faster pace, with new collaborative submission authoring, electronic transmission, regulatory intelligence, document management, and post-market surveillance features coming to the platform. We will also continue to expand our team with a new UK office to better serve the European market, and a number of new roles across the company. If you’re interested in helping medtech companies get lifesaving products to market more quickly, we’d love for you to join our team.
Learn more about Rimsys
We’d love to show you how the Rimsys RIM Platform can help medtech companies streamline processes across the regulatory lifecycle, strengthen global compliance, and get new products to market faster. Contact us to schedule a free custom demo.

RIM 101: what is regulatory information management?
Regulatory Information Management (RIM) refers to a category of software solutions that are designed to support and streamline the activities of regulatory affairs (RA) teams. For most teams they are a net-new category of software, and generally replace manual processes that are paper-based or run using traditional productivity software (spreadsheets and docs). RIM systems first emerged to support pharmaceutical regulatory activities, but in recent years medtech-focused solutions have hit the market as well.
Given their general new-ness, especially for medtech RA teams, it’s not surprising that many teams are unfamiliar with the technology. In our, admittedly informal, survey of RAPS 2021 attendees, only 11% of respondents said they currently use a RIM system, and 33% had no knowledge of the category at all. This article provides some background on what RIM systems are, and what they do to help medtech RA teams operate more effectively.

The role of regulatory affairs in medtech
To understand RIM systems, first we have to look at the role of regulatory affairs. In medtech, which includes medical devices, in vitro diagnostics, and medical software, RA teams play a critical role across a product’s lifecycle.
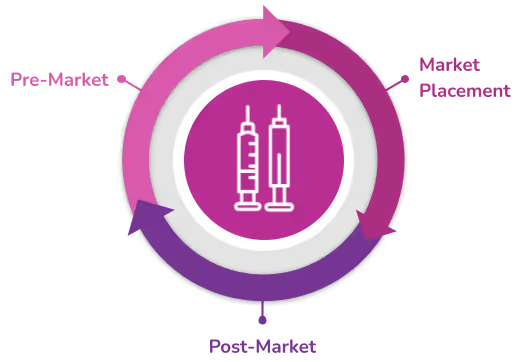
Before products are released for sale, RA teams work closely with research and development (R&D) teams to ensure that a new product meets necessary local requirements to be legally marketed in the desired target markets. There are over 113 different regulatory regimes around the world that medical devices are subject to. While there are many similarities, RA teams must understand the nuances between countries and guide R&D to ensure that products are developed accordingly.
Once products obtain market clearance, RA teams switch to monitoring mode to ensure that products can remain on the market. This includes keeping track of expiration dates and certificates, any changes in regulations or international standards that could impact the product, and any changes in the product or it’s technical documentation. Health authorities in many countries regularly perform product audits, so keeping all information in order and up-to-date is an important part of regulatory work.
RA teams usually take the lead on post-market surveillance activities as well, working closely with their quality assurance (QA) counterparts. They track adverse events and complaints, compiling this information from public and internal sources, and ensure that the data is reported appropriately to health authorities. Not all markets require extensive post-market surveillance for medical devices, but these regulations are becoming more common. Both the EU and Canada have recently implemented expanded surveillance requirements including the need for regular summary reporting to continuously confirm product performance and safety.
The information challenge
All of the regulatory activities highlighted in the previous section are repeated for every individual product the company sells in every regulated country or region. And, all of these activities are highly dependent on specific information. To do their jobs effectively, medtech regulatory affairs professionals need insight into global regulations and standards, detailed product specifications, testing, performance, and safety data, and a full record of all regulatory registrations and processes.
The problem is that this information is often scattered across the company. It’s stored in multiple systems, (sometimes physical) documents, and individual employees’ heads. Because this information is so scattered, RA professionals can spend up to 50% of their time just looking for things, and simple requests such as identifying whether a product has clearance to be marketed in a specific country can take days to complete.
How RIM systems can help
At a fundamental level, RIM systems are about helping RA teams corral and manage all of the information they need to do their jobs. RIM systems serve as a “single source of truth” for RA teams. They store and manage regulatory documents, integrate with systems across the company, and create a traceable record of all regulatory activities. All of this information is linked to individual products and countries or regions, making it much easier to find.
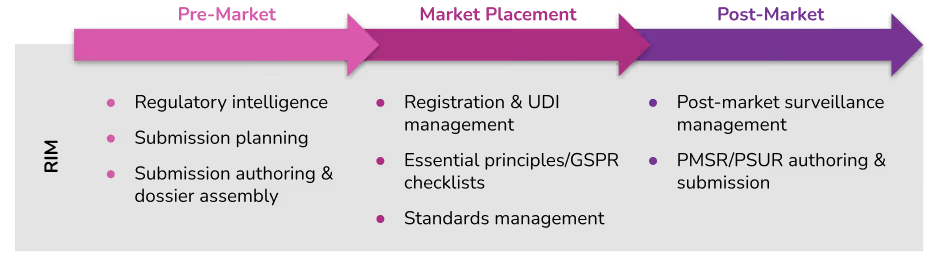
All of the collected information in a RIM system can be used to streamline regulatory activities across the product lifecycle. Before products are released, they provide access to regulatory intelligence, including market entrance requirements, that RA teams can use to guide product development and regulatory submissions. RIM systems also provide a collaborative digital hub where teams can author and assemble supporting documentation for new regulatory submissions.
For products currently on the market RIM systems can monitor registration expiration dates, and track changes in relevant standards and regulations to identify potential product impacts. This automated monitoring can give RA teams an “early warning”, and allow them to accommodate changes that might impact the selling status of a product.
RIM systems can also help with post-market surveillance activities. They can collect and centralize post-market data analytics, and facilitate planning and active surveillance activities to meet the most current regulatory requirements. These systems can also ensure that actions and conclusions drawn from the post-market surveillance process are consistently applied throughout the quality management system. And, the same authoring capabilities used to assemble pre-market submissions can be used for post-market reporting and communication with regional regulatory authorities.
Project planning, tracking, and management
Underpinning all of these capabilities is a full set of project features that allow RA teams to effectively manage and track their activities. This can include project request features that allow internal teams or 3rd-party partners such as local distributors to request specific regulatory activities or information. RIM systems also provide project task management, approval workflows, and digital signature capabilities that are fully auditable, and 21 CFR Part 11 compliant.
RIM systems also provide detailed reporting in the form of customized dashboards and registration, product, standards, and documentation reports. These reports offer at a glance monitoring of key information and detailed visibility into regulatory status and activities. For many teams this level of visibility is new, and allows them to fully measure, benchmark and report on their activities to company leadership.
The impact of RIM systems
RIM systems can have a tremendous impact on RA teams. By centralizing information they improve team productivity by ensuring that up-to-date information is always easily available and consistently applied. By automating workflows like new submission creation, or essential principles/GSPR table assembly they ensure that work gets done quickly and in-line with country/region requirements. RIM systems also provide more visibility into regulatory activities, allowing teams to benchmark and more accurately forecast the time required for new market clearance, and other product milestones.
To the company, the increased regulatory efficiency and effectiveness means reduced revenue risk from noncompliance or having to pull products from market, stronger, more confident global regulatory compliance, and ability to get new products to market much more quickly.
To learn more about RIM systems, their key capabilities, and if your organization could benefit from bringing one onboard, read our RIM System Buyer’s Guide for Medtech Companies.
