






The beginner's guide to the FDA De Novo classification process
This article is an excerpt from The beginner's guide to the FDA De Novo classification process ebook.
Contents
- Introduction
- Chapter 1: What is an FDA De Novo request?
- Chapter 2: Contents of a De Novo request
- Chapter 3: Submitting a De Novo request
- Appendix A: Acceptance review checklist
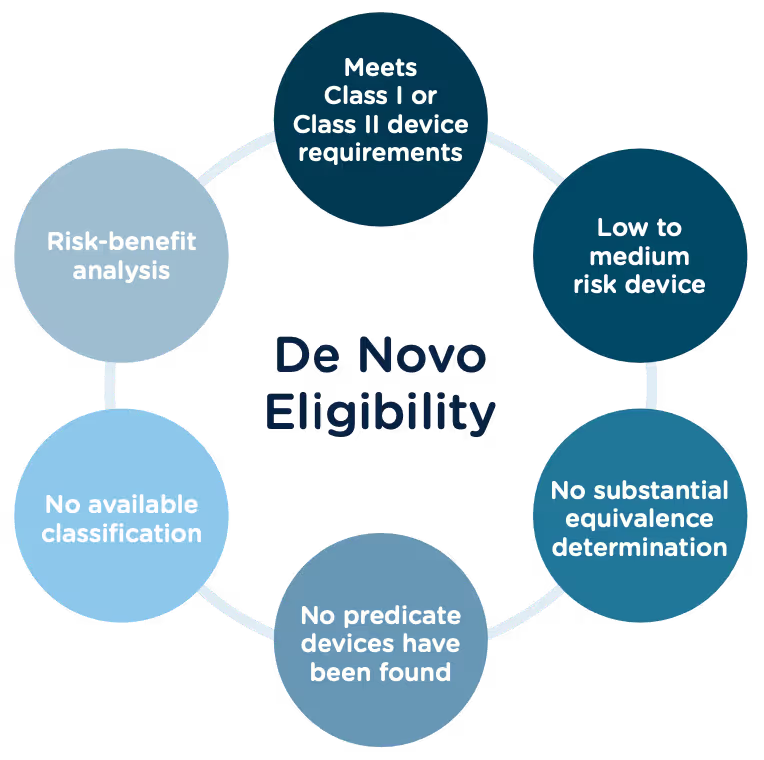
Congratulations, you have successfully developed a new medical device! Now you need to take it to market. Normally in the United States this would mean completing a 510(k) submission. However, the 510(k) relies on “substantial equivalence”—a comparison to a similar device already on the market (also called a predicate device) to assess the risk profile of the new device. What if your device is totally new, and there isn’t a similar device to compare it to? Enter the FDA De Novo process. The De Novo process provides a pathway to market for novel devices with a low to medium risk profile.
What does De Novo mean?
According to the Merriman-Webster dictionary, de novo is a Latin word meaning “as if for the first time; or anew.” Perfectly fitting that the FDA uses this term “De Novo” to describe market approval requests for new medical devices or technology where there is no comparable predicate device on the market.
The Food and Drug Administration Modernization Act of 1996 provided the FDA with the authority to create the De Novo Classification Process. It's a process that uses a risk-based strategy for a new, novel kind of medical device, in vitro diagnostic, or medical software solution whose type has previously not been identified and/or classified. It’s a process by which a novel medical device can be classified as a Class I or Class II device, instead of being automatically classified as Class III, which may not be appropriate. Before the implementation of the De Novo process in 1997, all the “not substantially equivalent” (NSE) products were required to be initially classified as a Class III device. But for a lot of devices, this risk class didn’t really make sense. The De Novo process provides a pathway for more accurate classifications of novel, lower-risk devices.
October, 2021, the FDA released a final guidance document "De Novo Classification Process (Evaluation of Automatic Class III Designation)" to provide guidance to the requester (also known as the manufacturer) and the FDA on the process for the submission and review of a De Novo Classification Request under section 513(f)(2) of the Federal Food, Drug, and Cosmetic Act (the FD&C Act). This process provides a pathway to an initial Class I or Class II risk classification for medical devices for which general controls or general and special controls, provide a reasonable assurance of safety and effectiveness, but for which there is no legally marketed predicate device. This guidance document replaced the "New Section 513(f)(2) – Evaluation of Automatic Class III Designation, Guidance for Industry and CDRH Staff" document, dated February 19, 1998.
Consistent with the final rule, the FDA updated the guidance documents below to provide recommendations for submitting De Novo requests, as well as criteria and procedures for accepting, withdrawing, reviewing, and making decisions on De Novo requests, effective January 3, 2022.
- User Fees and Refunds for De Novo Classification Requests
- FDA and Industry Actions on De Novo Classification Requests: Effect on FDA Review clock and Goals
- Acceptance Review for De Novo Classification Requests
The 510(k) and the De Novo processes are similar in that they are both pathways to market for medical devices with low to moderate risk, which is Class I and Class II. The biggest difference between the two is that the 510(k) heavily relies on the concept of "substantial equivalence" to an existing medical device. You must prove this to get the clearance of your 510(k) submission. In the De Novo process, there isn’t a product currently on the market that is “substantially equivalent” to yours, so it’s like starting with a clean slate. For more on the 510(k) process, see our Beginner’s Guide to the 510(k) ebook.
A result of the De Novo process to be aware of is that a successful submission will lead to a new predicate device type that someone else can reference to bring their product to market through the 510(k) process. You’ve done all the work, so now it’s available for anyone to use to provide "substantial equivalence".
De Novo history/timeline
Preparing a De Novo request
1. Do your research! Be sure to complete all the necessary research prior to your submission. You want to be sure that your device is not substantially equivalent to an existing device. Resources to review include:
- The Center for Devices and Radiological Health (CDRH)
- U.S. FDA Device Classification Database
- Device Classification Under Section 513(f)(2)(De Novo)
2. A De Novo request can be submitted with or without a preceding 510(k). There are two options for when you can submit a De Novo request:
Option A: After receiving a not substantially equivalent (NSE) determination (that is, no predicate, new intended use, or different technological characteristics that raise different questions of safety and effectiveness) in response to a 510(k) submission.
Option B: If you’ve determined, after extensive research, that there is no legally marketed device on which to base a determination of substantial equivalence.
3. Be sure all fees are paid to the FDA in advance of submitting a De Novo request. The FDA’s fiscal year begins in October and runs through the following September. Fees have increased each year since they were introduced, but the FDA’s percentage of reviews completed within the 150-day window has increased as well.
A business that is qualified and certified as a “small business” is eligible for a substantial reduction in most of the FDA user fees, including De Novo. The CDRH is responsible for the Small Business Program that determines whether a business is qualified.
Medical Device User Fee Amendments (MDUFA) guidance documents can provide more detailed information about all FDA user fees.
4. The initial request process serves only to determine if the De Novo request is administratively acceptable based upon the Acceptance Checklist. The initial acceptance is followed by substantive review which will determine the final risk classification of your device.
5. A Pre-Submission (Pre-Sub) is a formal written request for feedback from the FDA that is provided in formal written form, and then followed by a meeting. Although a Pre-Sub is not required prior to a De Novo request, it can be extremely helpful to receive early feedback, especially for devices that have not previously been reviewed under a 510(k). If you think you would like to submit a pre-sub first, there are suggested guidelines for submission you should consider:
- Describe your rationale for a Class I or Class II classification for your device.
- Provide the search results of FDA public databases and other resources used to determine that no legally marketed device and no classification for the same device type exists.
- Provide a list of regulations and/or product codes that may be relevant.
- Provide a rationale for why the subject device does not fit within and/or is different from any identified classification regulations, based on available information.
- Identify each health risk associated with the device and the reason for each risk.
- Briefly describe any ongoing and/or planned protocols/studies that need to be completed in order to collect the necessary data to establish the device’s risk profile.
- Provide information regarding the safety and effectiveness of the device. Cite the types of valid scientific evidence you anticipate providing in your De Novo request, including types of data/studies relating to the device’s safety and effectiveness.
- Briefly describe any ongoing and/or planned protocols/studies that need to be completed to collect the necessary safety and effectiveness data.
- Provide protocols for non-clinical and clinical studies (if applicable), including how they will address the risks you anticipate and targeted performance levels that will demonstrate that general controls or general and special controls are sufficient to provide reasonable assurance of safety and effectiveness.
- Share any proposed mitigation measure(s)/control(s) for each risk, based on the best available information at the time of the submission. Highlight which mitigations are general controls and which are special controls and provide details on each.
- Include any other risks that may be applicable, in addition to those identified in the Pre-Sub, given the indications for use for the device.
- If applicable, provide any controls that should be considered to provide a reasonable assurance of safety and effectiveness for the device.
- Provide any non-clinical study protocols that are sufficient to allow the collection of data from which conclusions about device safety and/or effectiveness can be drawn. These protocols should address whether the identified level of concern is the appropriate level of concern for the device software, and if any additional biocompatibility and/or sterility testing is required.
- If clinical data is needed, provide information to show that the proposed study design and selected control groups are appropriate?
6. The FDA will attempt to review the De Novo request submission within 15 calendar days of receipt of the request to make a determination that the submission is declined or accepted for review. If they are unable to complete the review within the 15 days, your submission will automatically move to “accepted for review” status. https://www.fda.gov/regulatory-information/search-fda-guidance-documents/de-novo-classification-process-evaluation-automatic-class-iii-designation
7. There are times when the FDA will refund your application fee. They have created a guidance document “User Fees and Refunds for De Novo Classification Requests” for the purpose of identifying:
- the types of De Novo requests subject to user fees
- exceptions to user fees
- the actions that may result in refunds of user fees that have been paid
When is a De Novo request subject to a user fee?
When will the FDA refund a De Novo user fee?
What fee must be paid for a new device submission following a De Novo “decline” determination?
To continue reading this eBook including a detailed walk-through of all the Traditional 510(k) components, submission requirements and timelines, and an overview of the other 510(k) forms including the Abbreviated 510(k) and the Special 510(k), please register to download the full version.



RAPS wrap-up
What a great conference! This year’s RAPS Convergence conference in Phoenix was outstanding by many measures. Not only was this the first time in quite a while that our community has had a chance to network in person, but our team also reported that the quality of conversations and presentations far surpassed their expectations. Kudos to the RAPS conference team for putting together a valuable and memorable experience.
We asked our team to share their thoughts about the conference, along with information they learned while attending sessions or in conversation with other RA professionals. We’ve compiled their thoughts below.
General thoughts on the conference
The consensus from our team was that this conference attracted a really good group of knowledgeable regulatory professionals and that the majority of sessions were incredibly informative. Everyone referenced great conversations they had throughout the conference.

There were a lot of discussions around the challenges that RA teams face today, and what can be done to ease the burden of regulatory professionals in the face of ever-changing requirements across the globe.
I was impressed by the consistently high level of quality in the conversations I had. Every person I spoke with had an intimate understanding of the challenges currently faced by industry and expressed a willingness to engage in conversation about how to improve things. While there are clearly significant challenges to overcome, I am bullish about the future.
James Trotter
And regulatory teams are looking for ways to be less reactive and find time for strategic planning to prepare for future challenges.
One of my biggest takeaways is the true shift in thinking that is happening within the industry in regard to the need to think strategically about supporting regulatory teams. In a number of conversations, it was mentioned that RA folks wished that they had more time to take a step back and have future-facing conversations, rather than just “keeping up” with their day-to-day activities.
Alex Tallentire
We noticed how well-attended the sessions were and heard comments from a number of people that they were having trouble deciding which sessions to attend. RAPS has made presentation slide decks available to attendees through the conference website.

Reggie, our regulatory duck, was also a big hit! Did you get one of our duck t-shirts?
Key session takeaways
CDRH Forum
The conversation was animated during the CDRH Forum, which ended with FDA stating “Communication is key. We take all feedback seriously and we are consistently making improvements.” Discussions centered largely around MDUFA V and the use of eSTAR templates. FDA is focusing on addressing the rising volumes of premarket submissions. This includes hiring additional reviewers, better support of 3rd party reviews to eliminate the need for FDA re-review, improved deficiency letter communication, and the expansion of electronic templates for submissions (including use with PMAs). They see these methods plus others as helping the agency meet the performance requirements on MDUFA V.
EU Regulations: PMCF and SSCP
Industry frustration - both by Notified Bodies and manufacturers - clearly continues over the burdensome requirements around PMCF and SSCP. As a subset of PMS, a PMCF plan is critical to MDR compliance and mandatory for Class III and implantable devices. Having a good plan is key, and industry is struggling to figure out what to do with the data once it is collected.
Because the audience for SSCP documents is healthcare professionals and patients, manufacturers will have to conduct readability assessments for each Summary of Safety and Clinical Performance (SSCP) through computer-based software programs or layperson assessments in all languages used in the EU market.
EUDAMED UDI
While the EUDAMED UDI module isn’t expected to be mandatory until the second quarter of 2026, there are triggering events that will require a manufacturer to enter data into the UDI module earlier. For example, mandatory use of the EUDAMED Vigilance module is Q4, 2024. If you have to report a product in the Vigilance module, that product must also be entered into the UDI module at that time. Bruce McKean, Rimsys Director of Regulatory, says that “Manufacturers cannot wait, they must be proactive rather than reactive when it comes to UDI.”
eSTAR
During the Solution Circle on “How to efficiently prepare your eSTAR submission,” attendees learned that FDA plans to expand the program to include more submission types. eSTAR submissions require a larger number of files attached to the PDF checklist, compared to the number of files submitted under traditional submission programs. One recommendation was to prepare your submission completely before filling out the eSTAR template. It seems apparent that the eSTAR program is designed to make the review process simpler for agency reviewers, but does not simplify the creation of the submission by the manufacturers.
If you are submitting a 510(k) to address a product change, the eSTAR template requires that all subsections be completed, even if they are not applicable to the change. This means that previously submitted and cleared information goes under review again. To avoid this, the recommendation was made that submitters include justification for not resubmitting data in these sections, rather than including the original data.
It is believed that the current guidance will be made final by the end of September 2022 with a one-year transition period for 510(k) and De Novo submissions.
What’s next?

RAPS has announced that next year’s conference will be in Montreal, October 3-5. We look forward to seeing everyone there (and we are working on next year's t-shirt design already). After this year’s great conference, we can’t wait to see next year’s!

FDA Class II medical devices
What are medical device classes within the FDA?
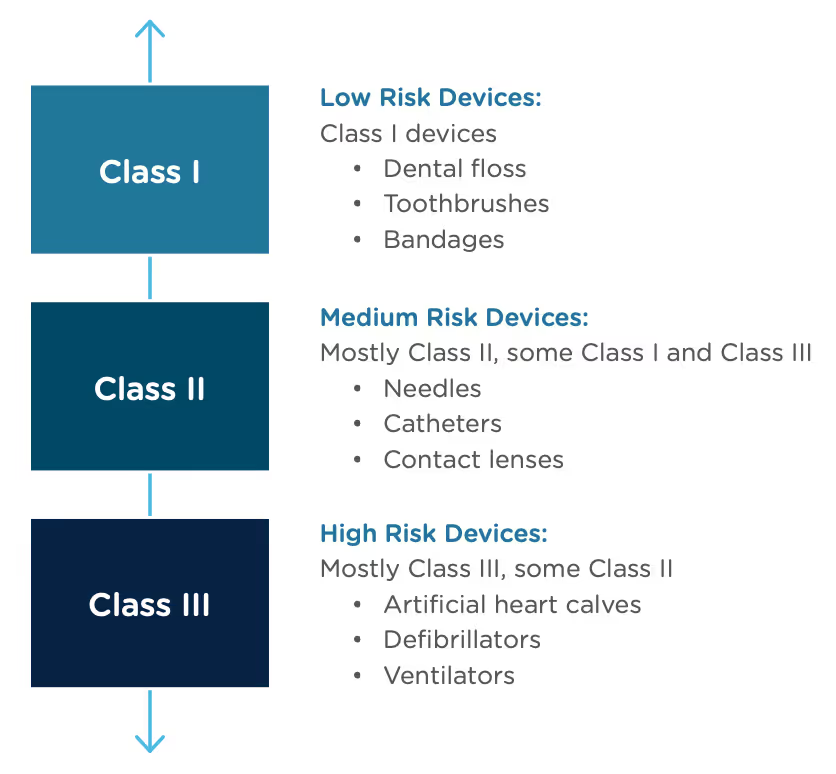
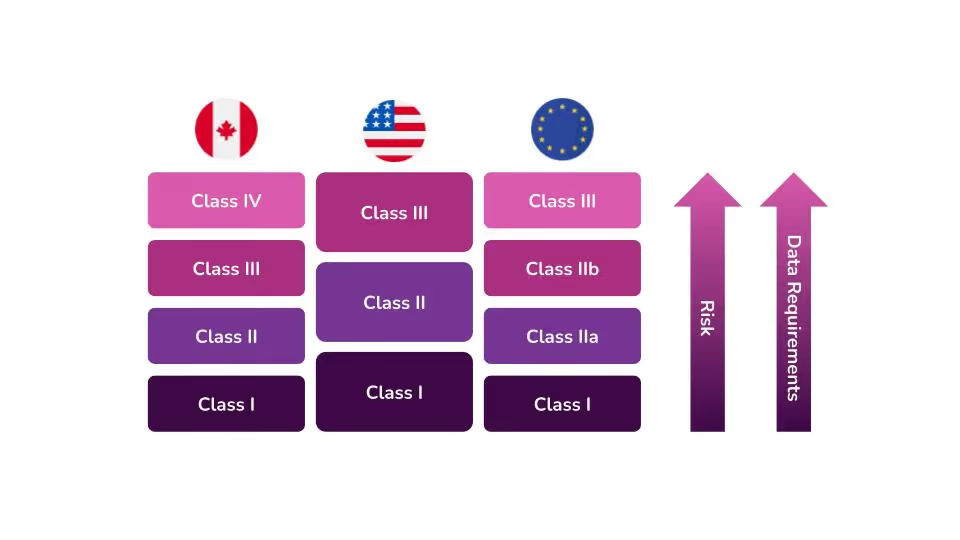
In the United States, the Food and Drug Administration (FDA) categorizes medical devices into three classes. They base these classes largely on the level of perceived risk the device may have. The level of perceived risk determines the data requirements and controls that need to be put into place to ensure safety for patients and/or users.
The FDA determines the level of oversight necessary for each device based on three factors. According to the FDA’s guidance on how to classify your device, device classification depends on the intended use of the device and also upon indications for use. The third and most important criterion is the device's risk to patients and users. The higher the risk associated with the device, the higher the class of that device will be, i.e Class I devices represent the lowest risk, and Class III devices pose the highest risk.
What are Class II Medical Devices?
Class II medical devices, which pose a medium to high risk to patients and users, account for 43 percent of all medical devices in the United States. Some common examples of Class II devices are syringes, pregnancy test kits, electric wheelchairs, and catheters. Class II medical devices must adhere to the provisions of the General Controls as mandated by the Food, Drug, and Cosmetic (FD&C) Act, which applies to all classes of devices.
The FDA also has its own Product Classification Database that can be used to assist in your device’s classification, finding consensus standards and submission types, such as a 510(k) or PMA.
What is the approval process for Class II Medical Devices?
All non-exempt Class II medical devices must go through the premarket notification process, also known as the 510(k). The 510(k) is a premarket submission process used to demonstrate that a device is safe and effective based on its substantial equivalence to a device already on the market, known as a predicate device.
Determining the substantial equivalence of your new device boils down to two things:
- Establishing that your device has the same intended use as the legally marketed predicate device
- Establishing that any technological differences between your device and the predicate device have no negative impact on the effectiveness and safety of the device
Any device with no identified predicate device, including those with a lower risk profile, is automatically classified as a Class III device and must use the more rigorous premarket approval (PMA) submission to receive market approval. Lower-risk devices can request reclassification, however, through a De Novo submission.
Class II medical devices in other countries
Device classification is different in each country. With that in mind, you should not make any assumptions regarding classification in other countries because your device is a Class II device in the United States. Each country with medical device regulations has its own classification scheme that may cause your device to be regulated differently.
During the initial phase of planning for the global commercialization of a product, it is imperative to consider international regulations, their classification schemes, and the registrations that each country will require.
The process of getting a Class II medical device to the market is arduous, and regulatory professionals must navigate disjointed manual data systems and processes. Plus, ever-evolving regulations make it difficult to ensure your new products, and even ones already on the market, are compliant.
Regulatory information management (RIM) software is an almost invaluable tool that can help your company get products to market more quickly and cost-effectively by digitizing and automating regulatory activities in a single system. The right RIM software can make the 510(k) process simpler and more efficient than ever before.
For more information on the 510(k) process, read our Beginner’s guide to the 510(k).

What's up with the duck?
If you’ve seen us online or at tradeshows, you might be wondering, “What’s up with the duck?” His name is Reggie by the way, and we’re pretty fond of him around here. Rimsys is more than software. It’s a team built from the ground up who understand the importance and challenge of managing regulatory affairs in the ever-evolving medical device industry. Our goal here at Rimsys is to help your company get its regulatory ducks in a row, and from that concept, “Reggie”, the regulatory duck was born.

If you could be a part of our company meetings, you’d see that we all love Reggie. After all, he’s more than a mascot to us. He symbolizes our mission to improve global health by accelerating delivery and increasing the availability of life-changing medical technologies. Reggie is our promise to our customers that you’re getting more than software with Rimsys. You’re getting a team of dedicated regulatory experts who understand the urgent need for better regulatory information and processes. That's why we love Reggie, our regulatory duck, and we believe you will too.

Brexit overview for medical device manufacturers
What is Brexit?
Brexit - meaning "British exit" is the process of the official withdrawal of the United Kingdom (UK) from the European Union (EU) on January 31, 2020, at 11:00 PM (GMT). The UK had been a member state of the EU since January 1, 1973, when it was known as the European Communities.
Leaving the EU was no easy task for the UK and it was six years in the making before it was final. When they “left” in January 2020, a discussion and negotiation transition period with the EU began. The negotiation process was both politically challenging and deeply isolating. Under the UK Prime Minister, Boris Johnson, the country continued to participate in many EU institutions during the one-year transition period in order to ensure frictionless trade until a long-term relationship could be agreed upon. Trade deal negotiations continued up until just days before the scheduled end of the transition period (December 31, 2020) and the EU–UK Trade and Cooperation Agreement was signed on December 30, 2020.
Following Brexit, EU law and the Court of Justice of the European Union no longer have power over British citizens and companies, with the exception of select areas related to Northern Ireland. Under the terms of the Brexit withdrawal agreement, Northern Ireland continues to participate in the European Single Market in relation to goods and to be a de facto member of the EU Customs Union.
The European Union Referendum Act 2015 set the wheels in motion. This Act of the Parliament of the United Kingdom made a legal provision for a referendum to be held on whether it should remain a member state of the European Union or leave it completely. The related legislation was introduced to the House of Commons in May of 2015, and it was passed on its third review in the House of Commons in early September 2015 and approved by the House of Lords in December 2015. The Act went into full legal force on February 1, 2016.
The initial withdrawal in March 2019 was delayed by the deadlock in the British parliament after the June 2017 general election. This deadlock then led to three extensions of the UK’s Article 50 of the Treaty of European Union (TEU), which began the member states’ withdrawal, known as Brexit.

Brexit’s effect on medical device regulations
All medical devices, including IVDs, custom-made devices, and systems or procedure packs must be registered with the UK’s Medicines and Healthcare Products Regulatory Agency (MHRA) before they can be placed on the UK market. The MHRA is developing a new regulatory framework for medical devices, designed to safeguard and advance the health of its people by enabling early access to a high-quality supply of safe, effective, and innovative medical products. CE marked devices will initially be recognized in the UK, but manufacturers will have to obtain UK Conformity Assessment (UKCA) certification and follow the marking requirements per UK MDR 2002, beginning July 1, 2023. CE-marked devices will be allowed in the UK market until June 30, 2023, as long as they have been CE marked under one of the following:
- Directive 90/385/EEC - active implantable medical devices
- Directive 93/42/EEC
- Directive 98/79/EC - in vitro diagnostic medical devices
- Regulation 2017/745
- Regulation 2017/746
Medical device manufacturers continue to be able to self-certify CE marked devices until June 30, 2023 - providing the certificates remain valid for the EU market under the transitional timelines listed in the EU MDR and IVDR.
From January 1, 2022, non-UK manufacturers will require a UK Responsible Person for the purposes of registering devices. A Northern Ireland-based Authorized Representative will no longer be able to register devices on a manufacturer’s behalf for Great Britain.
You will need to use the new UKCA marking before January 1, 2023, if your product:
- will be marketed in Great Britain, and
- is covered by legislation that requires the UKCA marking, and
- requires mandatory third-party conformity assessment, and
- conformity assessment has been carried out by a UK conformity assessment body.
This does not apply to existing stock if your goods were fully manufactured, CE marked, and placed on the market before January 1, 2021.
Northern Ireland – the rules are different
In some circumstances, it is a requirement of the UK MDR 2002 that you inform the MHRA when you first place your device on the Northern Ireland market. Under the Northern Ireland Protocol, different rules apply than those in Great Britain. The precise requirements depend on the location of the manufacturer, the location of the Authorized Representative, and the device class. For more information on the regulatory system for medical devices in Northern Ireland, refer to the Regulation of medical devices in Northern Ireland.
The future of medical device regulations under Brexit
As you can see, the rules have changed and may continue to be refined until June 30, 2023. Currently, the CE marking is only valid in the UK for areas where both UK and EU rules remain the same. The UKCA marking is not recognized in the EU market, therefore, products will need the CE marking to sell in the EU. The UK MDR 2002 is up to date with all changes known to be in force on or before June 28, 2022. However, there may be changes that will be brought into force at a future date.
For more information on the EU MDR and IVDR requirements, read our Ultimate guide to the EU MDR/IVDR unique device identifier (UDI) system and Ultimate guide to the EU MDR GSPR - general safety and performance requirements.

The RegUP rundown
What is a RegUP?
The medical device industry is, by its very nature, a high-stress one. New medical technologies are being created all the time, and as a result, regulations are constantly changing. Being a regulatory professional in the medtech industry requires extraordinary attention to detail and nerves of steel. Rimsys was founded by regulatory pros for regulatory pros, and we understand the need to unwind in a professional environment with other leaders in the industry. That’s why we came up with the idea of the RegUP.
So, what’s a RegUP? It’s short for “Regulatory Meetup,” and it’s a small gathering of regulatory professionals, not a large conference. We’ll enjoy delicious food and beverages as we get to know each other and discuss regulatory trends and best practices.
When and where?
Boston - Sept 29th
Our first RegUP event will be held on the East Coast in Boston, MA, on September 29, 2022, at Democracy Brewing. Democracy Brewing, nestled in historic Downtown Crossing (one of the oldest neighborhoods in the United States), is the first cooperative brewery in Boston. Their menu features plenty of delicious craft beers and an eclectic selection of cuisines ranging from Mediterranean to classic American bar food.
San Jose - Oct 13th
Our second event will be held on the West Coast in the San Jose area on Oct 13, 2022, at Big Dog Vineyards. Big Dog Vineyards is a locally owned and operated winery in the picturesque Milpitas Hills, CA. Their Winery & Tasting Room opened in 2009, right beside the estate vineyard, which was planted in 1997.
What should you expect at a RegUP event?
As mentioned, we understand that regulatory professionals in the medical device industry are under constant pressure to ensure they keep up with ever-changing trends and best practices. And if you are like us, the opportunity to hone your trade and sharpen your skills and knowledge in a more casual setting will be welcome.
Here’s the agenda for RegUP Boston to give you an idea of what to expect at our events:
- 12:00 - 12:30 pm Welcome: Increasing confidence in regulatory planning. Many regulatory challenges are driven by a lack of visibility into regulatory timelines, resources, and needs. A comprehensive regulatory data strategy can help RA teams build more resilient plans, and shift their organizational posture from reactive to proactive.
- 12:30 - 1:15 pm Catered lunch
- 1:15 - 1:45 pm TBD Regulatory best practices case study
- 1:45 - 2:15 MDR/IVDR information essentials: MDR/IVDR compliance remains top of mind for RA teams. New information requirements including GSPRs, UDI/EUDAMED, and Post-market surveillance and reporting require a new approach to regulatory information management.
- 2:15 - 4:00 pm Brewery tour, tasting, and networking
Rimsys Speakers
- James Gianoutsos - Founder & CEO
- Bruce McKean - Director of Regulatory (Boston)
- Adam Price - Director of Product, Post Market (San Jose)
We hope to see you there!
Our RegUP events in Boston and San Jose will be the first of many opportunities for us to network, further regulatory knowledge and processes, and even enjoy each other’s company over tasty beverages. Best of all, these events are free for Rimsys customers and qualified guests.
Of course, you can also expect these events to get bigger and better with time. Nonetheless, you don’t want to miss out on the first of these opportunities to get to know us and our industry better. We hope to see you there! If you are unable to attend though, keep an eye on our LinkedIn page for future RegUP events in a city near you.
To get more information and register for our upcoming events, click the links below:
- RegUP Boston: https://regup-boston.eventbrite.com/
- RegUP San Jose: https://regup-sanjose.eventbrite.com/

IVDR: In Vitro Diagnostic Regulation within the European Union
What is the IVDR In Vitro Diagnostic Regulation?
The European Union’s In Vitro Diagnostic Regulation (IVDR) 2017/746 applies to IVD devices and came into force on May 26, 2022. The IVDR is a major change over the In Vitro Diagnostic Directive (IVDD), which it supersedes. The new regulation is designed to better protect patients and address changes in IVD technology through new requirements and stricter controls. As a Regulation, unlike a Directive, the IVDR becomes a requirement in every EU country on the same day, which means that compliance with the IVDR is paramount for market access within the EU.
Major changes in the IVDR
The IVDR includes changes to IVD classification, increased documentation requirements, and UDI specifications. It is critical for manufacturers and their European representatives to understand and implement the new regulations as soon as possible. There is significant concern that notified bodies will not have sufficient resources to handle the increased need for their services.
The major changes between the IVDR and its predecessor, IVDD, are as follows:
Changes to the classification system
Under the IVDD only a small percentage of IVD products were assigned a higher risk classification (based on a predefined list of products). All other products were exempt from notified body oversight and allowed for manufacturers to self-certify through conformity procedures. Under the IVDD, only 10%-20% of IVD products were subject to notified body oversight, whereas, under the IVDR, 80%-90% of IVD products will be subjected to notified body oversight.
Unlike the IVDD, the IVDR defines 4 risk classes based on risk profile:
- Class A: Lowest risk (e.g. specimen containers)
- Class B: Low to moderate risk (e.g. pregnancy tests)
- Class C: Moderate to high risk (e.g. cancer screening products)
- Class D: High risk (e.g. HIV tests)
It is important that IVD manufacturers re-classify their products using the new classification rules as soon as possible. Notified body oversight is required for IVDs in class B through class D.
Increased technical documentation requirements
Under the IVDD, technical documentation requirements were vague and left largely to the discretion of the manufacturer. The IVDR, however, details specific requirements for the content of technical documentation. Annex I details the General Safety and Performance Requirements, Annex II details primary technical documentation requirements, and Annex III details requirements for technical documentation for post-market surveillance.
Unique Device Identification (UDI) requirements
IVDs now require UDI labeling and registration in the European Union Database of Medical Devices, more commonly known as EUDAMED, in the same way as other medical devices. A UDI must be assigned to all medical devices, with some exceptions for custom-made and investigational devices.
Each UDI consists of multiple elements, including a Basic UDI-DI (also known as “BUDI”), a device identifier (DI) with static device information, and a product identifier (PI) with dynamic information provided by the manufacturer (such as serial number and manufacturing date). In addition, manufacturers can now register their device in EUDAMED, though this is not yet required.
Quality management system requirements
All IVD manufacturers are expected to have a quality management system in place, even though only those manufacturing class B to D devices require certification of conformity assessments by a notified body.
Person Responsible for Regulatory Compliance (PRRC)
Manufacturers will now be required to designate at least one person to monitor compliance with regulatory requirements. A PRRC must be qualified by way of a relevant degree and a minimum of one year of professional experience, or at least 4 years of experience in medical device regulatory affairs or quality management. Note that smaller manufacturers do have the option to subcontract their PRRC functions, but one person cannot act as a PRRC for a manufacturer based outside of the EU and for an Authorized Representative.
IVDR deadlines
Manufacturers who were able to self-declare conformity under the IVDD, but require a notified body under IVDR may continue to place IVDs on the market assuming they had issued a declaration of conformity prior to the original May 26, 2022 deadline, introduce no significant changes to the product, meet all post-market surveillance and vigilance requirements, and register in EUDAMED as specified in the IVDR. Assuming that these requirements are met, the new transition dates are as follows:
- May 26, 2022 - All new devices and non-sterile self-declared devices
- May 26, 2025 - Class D devices
- May 26, 2026 - Class C devices
- May 26, 2027 - Class B devices and Class A sterile devices
IVD regulations outside of the EU
This article is specific to requirements in the EU. It is important to note that other countries, such as the United States, have their own regulations related to In Vitro Diagnostics that are covered by the country’s medical device regulations. Each country with medical device regulations has its own classification scheme that may cause your device to be regulated in a different way. During the initial phase of planning for global commercialization of a product and throughout the product life cycle, it is imperative that you consider international regulations, their classification schemes, and the registrations that each country will require.
For additional information, The ultimate guide to EU MDR and IVDR general safety and performance requirements and also The Ultimate Guide to EU MDR/IVDR UDI.
