



The ultimate guide to the medical device single audit program (MDSAP)
This article is an excerpt from The ultimate guide to the medical device single audit program (MDSAP) ebook.
Table of contents
- What is MDSAP?
- History of MDSAP
- Who is responsible for the MDSAP?
- How does an MDSAP audit work?
- Audit sequence
- You got a nonconformity – now what?
- What does an MDSAP audit cost?
- Why choose the MDSAP certification process?
- Potential disadvantages of the MDSAP
- Ready to participate? – Here’s how to get started
- Completing a successful MDSAP audit
The Medical Device Single Audit Program (MDSAP) was designed and developed to allow a single audit of a medical device manufacturer to be applied to all country markets whose regulatory authorities are members of the program. The MDSAP provides efficient and thorough coverage of the standard requirements for medical device manufacturer quality management systems, and requirements for regulatory purposes (ISO 13485:2016). In addition, there are specific requirements of each medical device regulatory authority participating in the MDSAP that must be met:
- Conformity Assessment Procedures of the Australian Therapeutic Goods (Medical Devices) Regulations (TG(MD)R Sch3)
- Brazilian Good Manufacturing Practices (RDC ANVISA 16)
- Medical Device Regulations of Health Canada (ISO 13485:2003)
- Japan Ordinance on Standards for Manufacturing Control and Quality Control of Medical Devices and In Vitro Diagnostic Reagents (MHLW Ministerial Ordinance No 169)
- Quality System Regulation (21 CFR Part 820), and specific requirements of medical device regulatory authorities participating in the MDSAP program.
This means that a report from a single MDSAP audit of a medical device manufacturer would be accepted as a substitute for routine inspections by all the member Regulatory Authorities (RAs) across the world. There are currently five participating Regulatory Authorities (RA) representing the following countries: Australia, Brazil, Canada, Japan and the USA.

In April, 2021, the RAs released an “Audit Approach” document (MDSAP AU P0002.006) that combines the formerly separate MDSAP Audit Model and Process Companion documents into a single guidance document. It includes guidance for assessing the conformity of each process and includes an audit sequence, instructions for auditing each specific process, and identifies links that highlight the interactions between the processes.
In March 2012 the US FDA announced that they had approved a final pilot guidance document “Guidance for Industry, Third Parties and Food and Drug Administration Staff: Medical Device ISO 13485:2003 Voluntary Audit Report Submission Pilot Program.” This allowed the owner or operator of a medical device manufacturing facility to be removed from FDA’s routine inspection work plan for 1 year upon completing a ISO 13485:2003 audit. This guidance document went into effect in June 2012, and was intended as an interim measure while a single audit program was being developed.
This pilot program was not very successful and few companies signed up because they did not see any advantage in participating. The manufacturer had to pay for a third party to inspect their facilities, generate a report, and share the inspection results back to the FDA. Many companies were reluctant to contract “someone else” to perform their inspection when they could easily wait for the FDA to conduct an inspection for free.
During its inaugural meeting in Singapore in 2012, the International Medical Device Regulators Forum (IMDRF) appointed a working group to develop a set of documents for a harmonized third-party auditor system. Hence, the “Medical Device Single Audit Program” (MDSAP) was formed. The concept was similar to the FDA’s original idea of creating a third-party auditor to help reduce their workload of performing regulatory audits of medical device manufacturers’ quality management systems. This new approach would consist of a single audit that would review regulatory QMS compliance, conducted by a third-party, who would later be called an Auditing Organization (AO).
From January 2014 to December 2016, five countries participated in a Medical Device Single Audit Program Pilot. In June 2017, a report was generated summarizing the outcomes of prospective “proof- of-concept” criteria established to confirm the success of the program. The outcomes are documented in the final MDSAP Pilot Report and recommended that the program become fully active and open to any manufacturer who requested this type of audit.
The governing body of the MDSAP is the Regulatory Authority Council (RAC), which is composed of two senior managers (and a few other staff members) from each participating RA. They are responsible for executive planning, strategic priorities, setting policy, and making decisions on behalf of the MDSAP International Consortium. The RAC also reviews and approves documents, procedures, work instructions, and more. The mission of the MDSAP International Consortium is to jointly leverage regulatory resources to manage an efficient, effective, and sustainable single audit program focused on the oversight of medical device manufacturers on a global scale.
Other international partners that are involved in the MDSAP include:
MDSAP Observers:
- European Union (EU)
- United Kingdom’s Medicines and Healthcare products Regulatory Agency (MHRA)
- The World Health Organization (WHO) Prequalification of In Vitro Diagnostics (IVDs) Program
MDSAP Affiliate Members:
- Argentina’s National Administration of Drugs, Foods and Medical Devices (ANMAT)
- Republic of Korea’s Ministry of Food and Drug Safety
- Singapore’s Health Sciences Authority (HSA)
The observers and affiliate members are not the same as the participating member RA’s. The observers simply observe and/or contribute to RAC activities. Affiliate members, on the other hand, are interested in engaging in the MDSAP program and are subject to certain rules. They are only given access to a certain level of information about the manufacturers, audit dates, and information in audit reports.
They are also invited to attend sessions that are open to members, observers, and affiliates only.
Audits can also be conducted by MDSAP participating RAs at any time and for various reasons including:
- "For Cause" due to information obtained by the regulatory authority
- as a follow up to findings from a previous audit
- to confirm the effective implementation of the MDSAP requirements
The purpose of audits conducted by the RAs is to ensure appropriate oversight of the AOs MDSAP auditing activities. The AOs are appointed by the RAs and a list of the currently approved AO’s is published on the FDA website. Most AOs offer a broad range of management system certification services, beyond just medical devices. Manufacturers should verify that prospective AOs are clearly trained and perform MDSAP audits of medical devices.
AOs have the final word as to whether a manufacturer has met the requirements for the MDSAP during the execution of the audit and generation of the associated reports summarizing the results. MSDAP RAC participating RAs have the final decision regarding all development, implementation, maintenance, and expansion activities associated with the program.
Although an unannounced visit by an AO is rare, it can happen in circumstances where high-grade nonconformities have been detected.
To continue reading this eBook including a detailed look at the MDSAP audit process and grading, pros and cons of the approach, and how to get started please register to download the full version.

The beginner's guide to the FDA 510(k)
This article is an excerpt from The beginner's guide to the 510(k) ebook.
Table of Contents
- Introduction
- 510(k) basics
- Contents of a Traditional 510(k)
- 510(k) submission and timelines
- Other 510(k) forms
Congratulations! You have successfully developed a new medical device. Now you need to take it to market. In the United States, this often means submitting a 510(k). A 510(k) is a structured package of information about your device and its performance and safety that you submit to the Food and Drug Administration (FDA) for “clearance” before you can sell your device in the U.S. In order to receive clearance from the FDA, your 510(k) will need to demonstrate that your medical device is substantially equivalent to another legally marketed device (called a predicate device). The substantial equivalence approval process is a simple equation that looks something like this:

The 510(k) is generally the most efficient route to market clearance in the U.S. because you show your device is safe and effective based on this substantial equivalence standard, instead of needing to present more extensive clinical trial data.
There are three types of 510(k): Traditional, Abbreviated, and Special. This eBook will begin with a general overview of the 510(k) process, including its purpose and benefits. Next, we will explore the Traditional 510(k) and the sections and components required in depth. Finally, we will look at the Special and Abbreviated 510(k).
FDA: background and device oversight
Before we explain what a 510(k) is let’s first talk generally about the FDA and device oversight. The FDA is the U.S. governmental agency responsible for overseeing medical devices, drugs, food, and tobacco products. When it comes to medical devices, the FDA’s mission is to “protect the public health by ensuring the safety, efficacy, and security of…medical devices.” At the same time, the FDA also has an interest in “advancing public health by helping to speed innovations.” In other words, the FDA’s goal is to make sure devices are safe and effective for public use, while also ensuring that devices have a quick and efficient path to market.
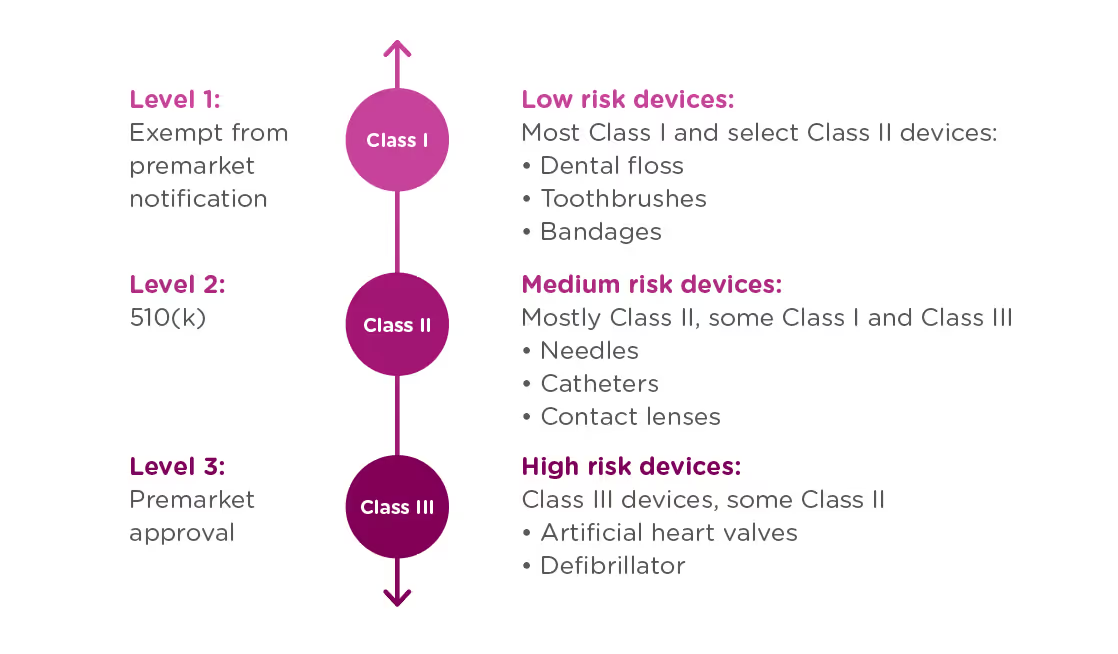
In order to achieve this balance of safety and efficiency, the FDA has three different levels of oversight depending on the risk level of the device: (1) exempt from premarket submission, (2) Premarket Notification, also known as 510(k), and (3) Premarket Approval (PMA).
When is a 510(k) required?
A 510(k) is required for medium risk devices that have a predicate on the market which can be used to demonstrate the safety and effectiveness of the new device. Meanwhile, a PMA is required for high-risk or novel devices which require a higher level of scrutiny to be confirmed safe and effective.
A 510(k) is not only required for new devices, but also for devices that have been modified in a way that could impact safety or effectiveness. This could include changes to the:
- Design
- Components
- Materials
- Chemical composition
- Energy source
- Manufacturing process
- Intended use
You must submit your 510(k) at least 90 days before marketing the device.
What Exactly is Substantial Equivalence?
Now that we know what a 510(k) is, let’s talk about the substantial equivalence standard. You’ll recall from the introduction that your 510(k) must show that the new (or modified) device is substantially equivalent to at least one other legally marketed device, called a predicate device. Substantial equivalence looks at the intended use and the technological characteristics of the two devices.
More specifically, you must show:
- that the new device has the same intended use as the predicate, and
- the differences between the two devices do not raise questions about the safety and effectiveness of the new device.
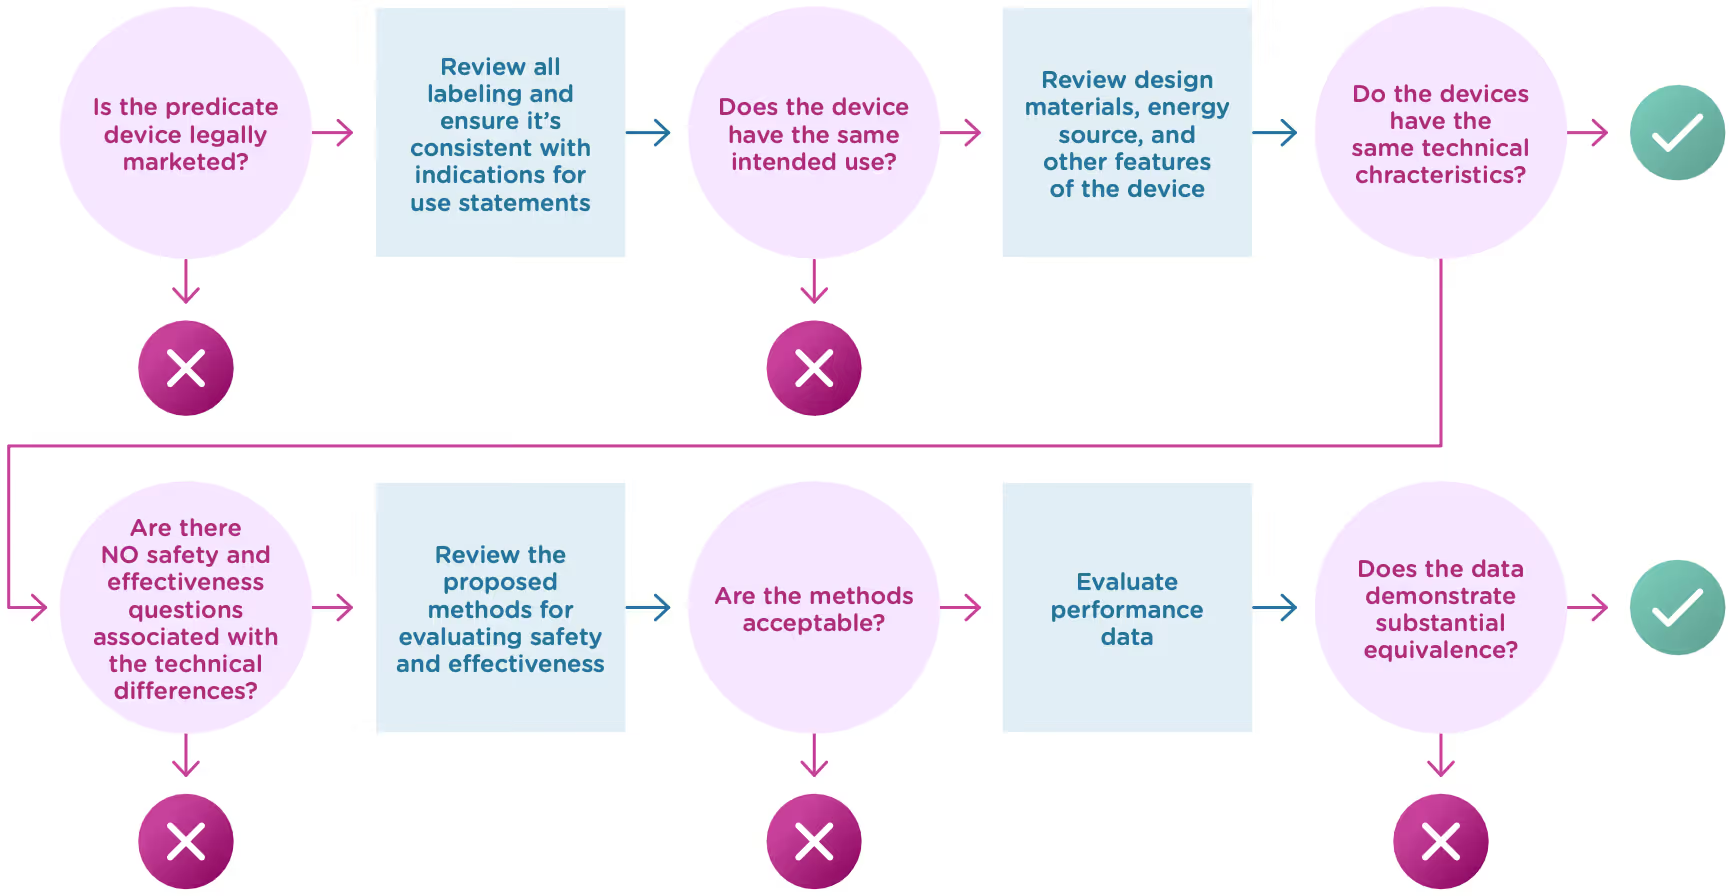
Now let’s take a closer look at intended use and technological characteristics.
Intended use
Intended use means the general purpose or function of the device. The FDA will look at your proposed labelling and your Indications of Use section of the 510(k) to determine the intended use of your device (this is covered in Chapter 2). Intended use includes:
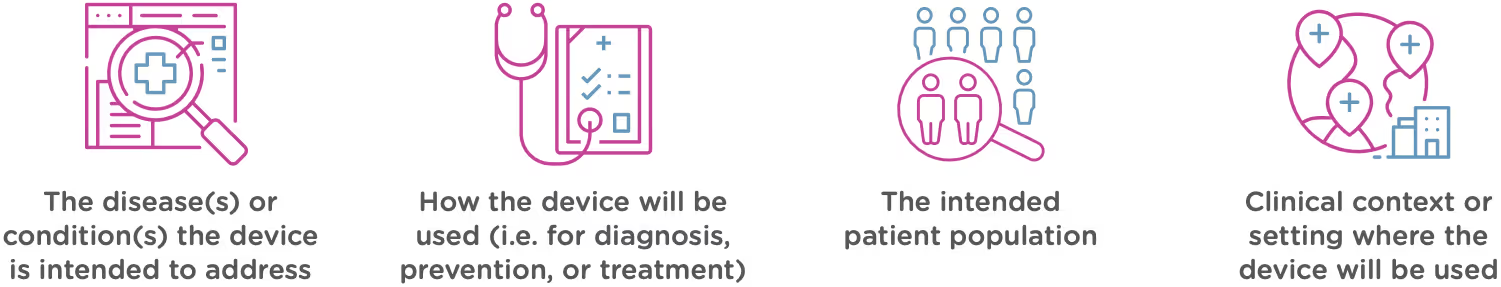
Technological characteristics
Once the FDA has determined that a predicate device exists and that the new device and the predicate device have the same intended use, it will move on to compare the technological characteristics. Technological characteristics include:
- Materials
- Design
- Energy source
- Other device features
The two devices do not have to be identical, and in fact they almost never are. The key here is to demonstrate that any differences do not have a significant impact on safety or effectiveness. Here’s what to cover when you compare your device’s technological characteristics with that of the predicate device:
Overall description of the device design
- Engineering drawings or diagrams to explain the device and component parts.
- List of component parts and explanation of how each component contributes to the overall use and function of the device.
- Physical specifications: dimensions, weight, temperature, tolerances, etc.
Materials
- Detailed chemical formulation used in all materials of constructions (especially those that come into contact with a patient).
- Any additives, coatings, paint, or surface modifications.
- How materials have been processed and what state they’re in.
Energy Sources
- Use of batteries, electricity, etc.
Other technological features
- Software/hardware
- Features
- Density
- Porosity
- Degradation characteristics
- Nature of reagents
- Principle of the assay method
In deciding whether the differences in technological characteristics impact safety or effectiveness, the FDA will typically rely on descriptive information about the technological characteristics as well as non-clinical and clinical performance data.
Let’s look at an example: A manufacturer submits a 510(k) for a new type of contact lens. Both the new device and the predicate device are indicated for daily wear for the treatment of astigmatism. The predicate device is only available in a clear lens, but the new device comes in a line of colors, including purple tinted lenses.

Who is responsible for submitting a 510(k)?
The following four types of organizations may be responsible for submitting a 510(k):
Manufacturers
- End-of-line device manufacturers who will be placing a device on the U.S. market.
- Note: Does not apply to component part manufacturers unless components will be marketed independently.
Specification developers
- Companies that develop the specifications for a finished device which has been manufactured elsewhere
Repackers or relabelers
- Required to submit a 510(k) if they significantly alter the labeling or condition of the device, including modification of manuals, changing the intended use, deleting or adding warnings, contraindications, sterilization status.
- Note: This is rare. The manufacturer, not the repackager or labeler, is typically responsible for the 510(k) submission.
Importers
- Importers that introduce a new device to the U.S. market may need to submit a 510(k), if it hasn’t already been submitted by the manufacturer.
Now that we’ve covered the basics, let’s explore what actually goes into your 510(k).
A Traditional 510(k) should contain all the following components in the list below. In some cases, a particular section may not apply to your device. When that happens, it’s a good idea to include the section anyway and just state “This section does not apply” or “N/A” under that heading.
To continue reading this eBook including a detailed walk-through of all the Traditional 510(k) components, submission requirements and timelines, and an overview of the other 510(k) forms including the Abbreviated 510(k) and the Special 510(k), please register to download the full version


The ultimate guide to the China UDI system and database
This article is an excerpt from The ultimate guide to the China NMPA UDI system and database ebook.
Table of Contents
- Overview
- UDI basics and benefits
- UDI format requirements and issuing entities
- UDI database and submission requirements
- Implementation of UDI and the UDI database in China
The current Chinese medical device regulatory regime kicked-off in 2014 with the Regulation on Supervision and Administration of Medical Devices. This core set of registration requirements, modeled after the United States and European Union systems, established a set of device classifications (class I, II, and III) based on risk and procedures for obtaining market clearance for each type of device.
Medical devices in China are regulated by the National Medical Products Administration (NMPA). Class I devices, such as clinical laboratory equipment or non-invasive skin dressings, require only notification to the NMPA for marketing authorization, and that authorization does not expire. Class II and III devices such as implantable devices or devices with a measuring function require full registration and a formal review before market clearance can be obtained.
These initial regulations have been expanded since their introduction, adding accelerated pathways to market for certain products in certain regions, easing acceptance of clinical data from overseas, and more specific roles and responsibilities for local agents of international manufacturers. In addition, in 2019, the regulations added a provision that medical devices carry a unique device identification (UDI). China’s UDI requirements are similar to those in the US and European Union. They establish specific device ID and labeling requirements, as well as a central, state-administered database of devices.
This eBook walks through the basics of medical device UDIs, the specifics of China’s implementation, and how MedTech companies who market their devices in China can prepare for the full rollout of these regulations in the coming years.
A UDI is a unique alphanumeric code that is designed to identify medical devices sold in a particular country/region from manufacturing, through distribution, to use by a patient. Like other aspects of the medical device regulatory regime, the UDI system in China follows the approach taken by the United States FDA and European Commission, and is based on the guidance from the International Medical Device Regulators Forum (IMDRF). Generally, UDI systems are designed to improve patient safety and optimize care by:
- Increasing the traceability of medical devices, including field safety corrective actions
- Providing an unambiguous identification method for medical devices throughout distribution and use
- Making adverse event reports more accessible
- Reducing medical errors by providing detailed information related to the device
- Simplifying medical device documentation and making it more consistent
There are three components to the UDI system in China:
- UDI code: The actual UDI code can be assigned by one of three (3) issuing agencies and contains information about the product, it’s expiration date, and the manufacturing batch/lot it’s associated with.
- UDI labeling: Put simply, medical devices must carry the UDI code on them. The regulations stipulate how devices and their packaging must be labeled for compliance.
- UDI database: In addition to labeling, all device UDIs must be submitted to a central database that is administered by the NMPA.
The following sections explore each of these components in more detail.
The UDI code
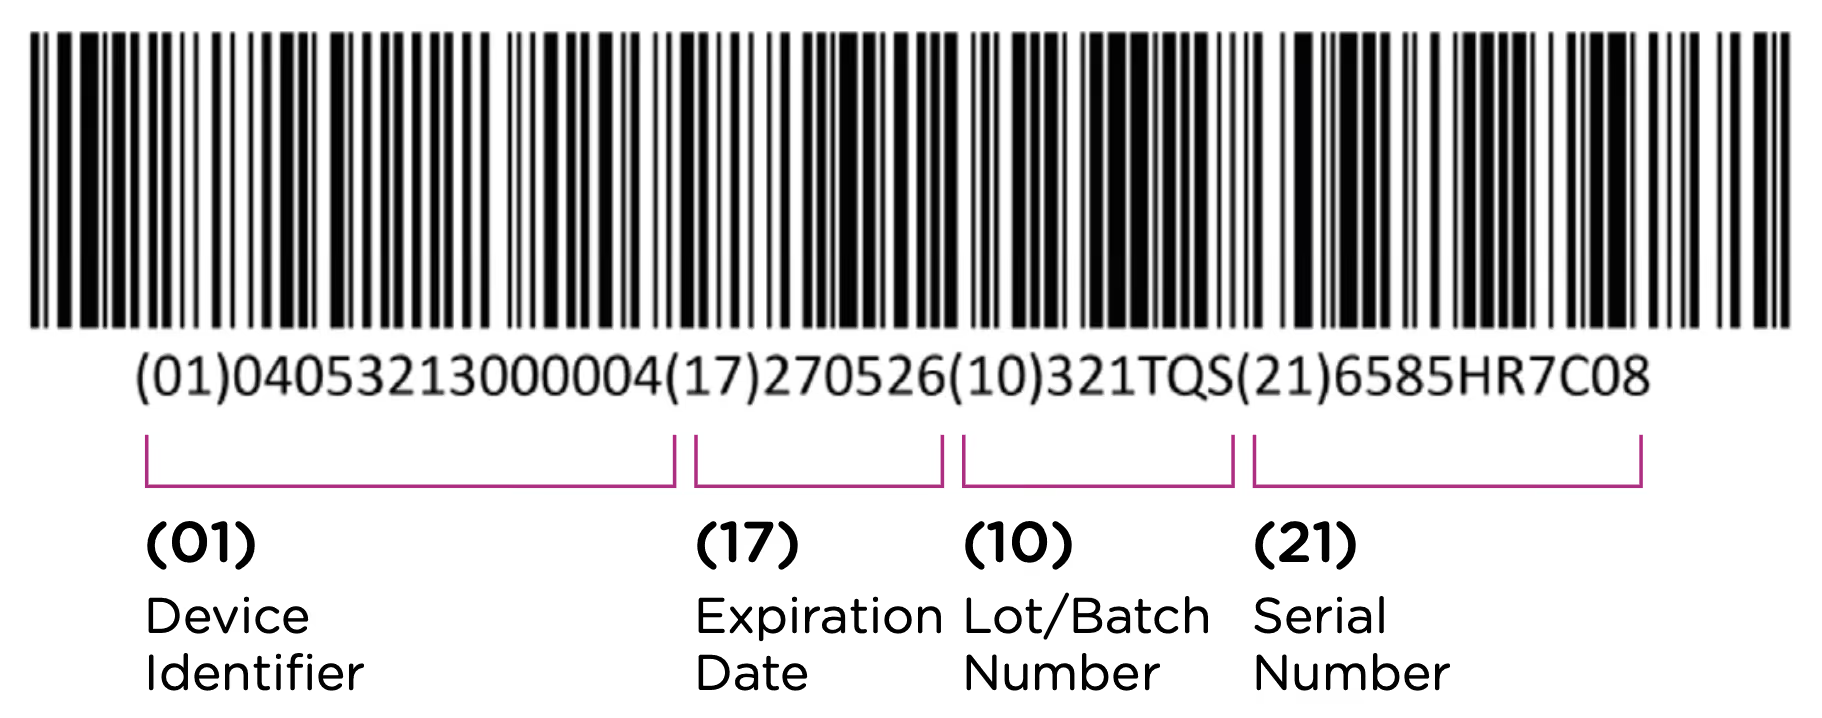
The first element of the UDI system is the code itself. The UDI code is the alphanumeric identifier that is associated with a specific medical device. UDI codes have two (2) elements to them, the UDI device identifier (UDI-DI) or static portion, and the UDI production identifier (UDI-PI) or dynamic portion. You can see the two components in the UDI diagram below:

The UDI-DI contains information about the issuing entity—the organization that is authorized to assign UDI codes. In China, this can be one of three entities: GS1, an international barcode and electronic data interchange standards organization, and two domestic organizations: the Zhongguancun Industry & Information Research Institute (ZIIOT), and AliHealth. Additional details about the issuing agencies are covered in Chapter 2. In addition, the UDI-DI contains information about the manufacturer and the specific model or version of the device.
The UDI-PI contains information about the manufacturing and production of the device. This typically includes information about the lot or batch number in which the device was manufactured, the manufacturing date and expiration date for the device (if applicable), and the specific serial number for the device. Here you can see all of the components marked up using the same UDI example:
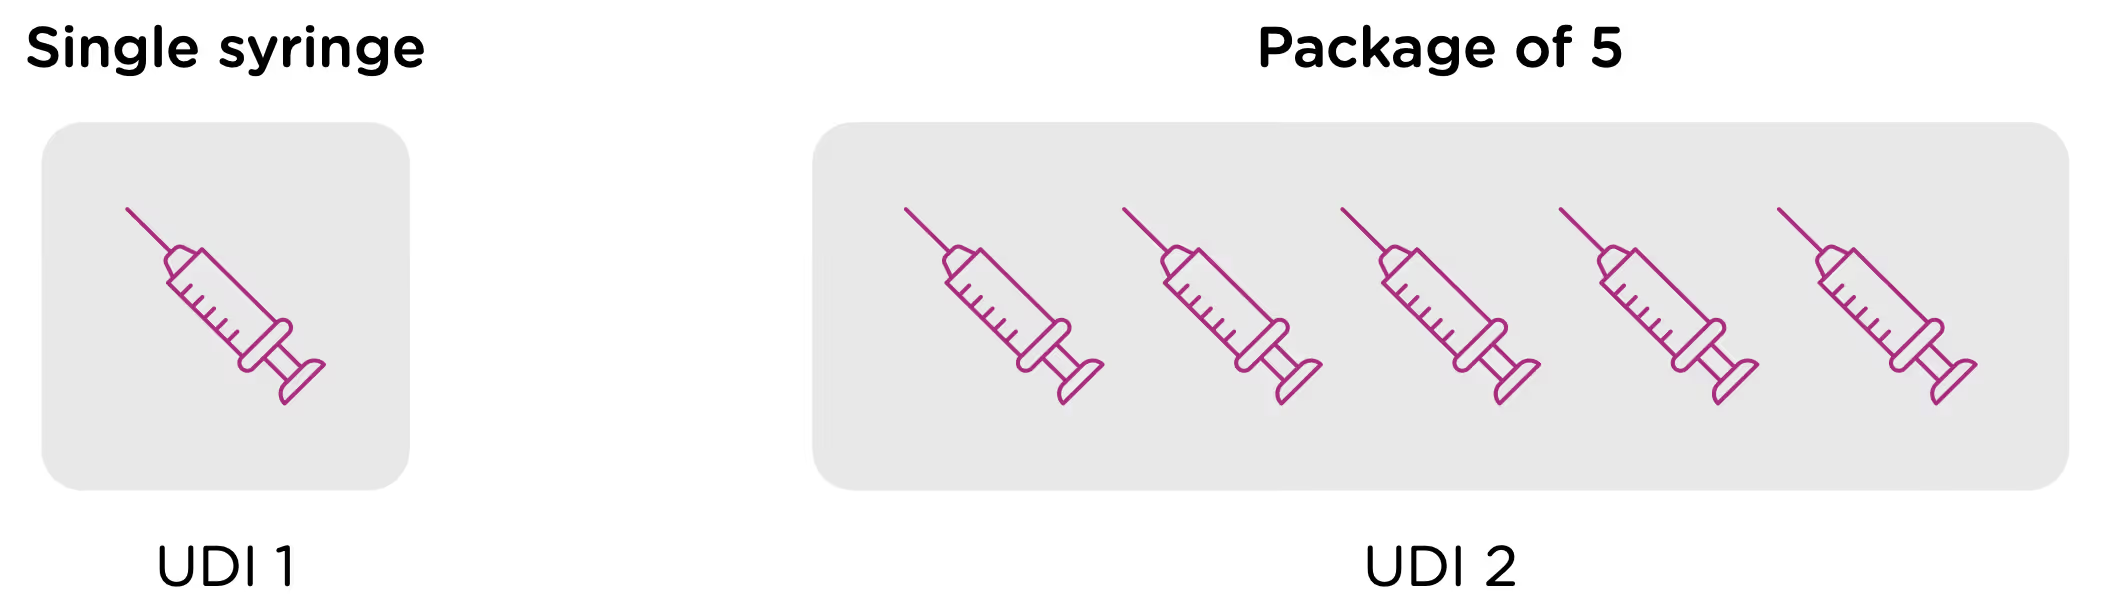
Note that each packaging permutation and level for a given device will need to be assigned its own UDI. So for example, let’s say that a company manufactures 5ml enteral (oral) syringes in two packaging options: 1 – packaged individually and 2 – packaged in a box of 5. Each packaging option would need its own UDI, despite the fact that the underlying product is the same.
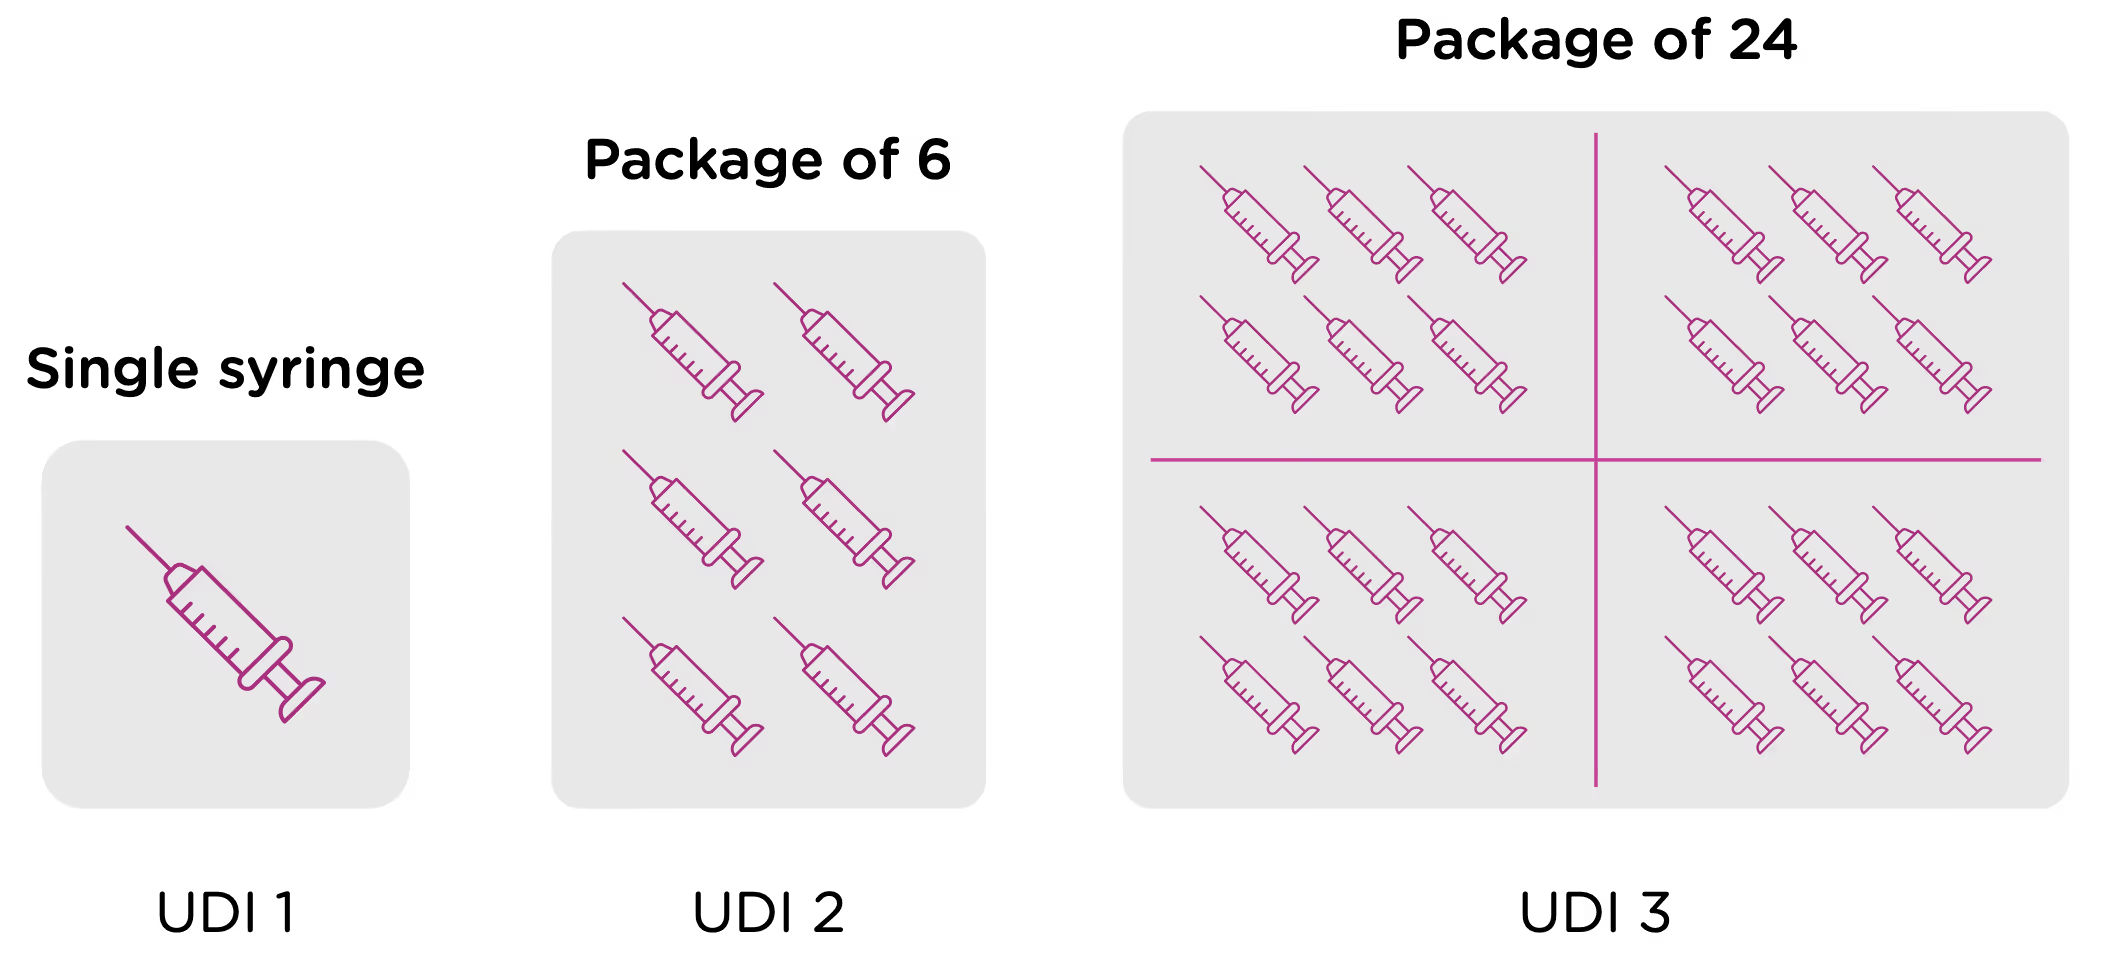
Now looking at packaging levels, let’s assume that the manufacturer packages the single syringe offering into boxes of 6, and again into larger containers of 24. Each of those packaging options needs its own UDI as well.
Labeling
In addition to obtaining UDI code for each device as outlined in the previous section, medical device manufacturers are required to ensure that devices are appropriately labeled with the assigned UDI. This label is called the UDI Carrier. The UDI is represented in two forms on the UDI Carrier: a machine-readable form and a human-readable form.
The machine-readable form or automatic identification data capture (AIDC) is a barcode or some other technology that can be used to automatically capture UDI information. The NMPA regulations support 3 types of machine-readable formats: 1-dimensional barcode, 2-dimensional barcode, and radio-frequency identification (RFID).

The regulations note that “use of advanced automatic identification and data collection technologies is encouraged”—prompting manufacturers to use more modern 2D and RFID machine-readable carriers where possible. Note, however, that if a device uses RFID, the UDI Carrier must also include the UDI in barcode format.
The human-readable form or human-readable interpretation (HRI) is the numeric or alphanumeric code for the UDI that can be read and manually entered into systems.

The UDI Carrier should be included on the device and on all levels of packaging. The UDI Carrier must be clear and readable during the operation and use of devices. If there isn’t room on the device for both the human and machine-readable forms of the UDI, then manufacturers should prioritize the machine-readable form.
UDI database
The third component of the NMPA UDI system is the UDI database. This is a centralized database of UDI and product information, administered by the NMPA. Manufacturers are required to submit UDI information into the database within 60 days after a product is approved (for sale in China) and before it is commercialized. The database contains a more detailed product record than what is included in the UDI itself, and it is the responsibility of the manufacturer (and/or their in-country representative) to submit the information correctly, and ensure that it’s kept up to date.
Chapter 3 of this eBook goes into detail about the specific fields and data requirements for UDI database submissions.
To continue reading this eBook including information about UDI format requirements and issuing entities, implementation timelines, and affected device types, please register to download the full version.


STED is dead
What is STED?
The STED, or Summary of Technical Documentation, format was created originally by the Global Harmonization Task Force (GHTF), the precursor to the current International Medical Device Regulators Forum (IMDRF). The original STED format, defined in 2007, was the first attempt to harmonize medical device submission information and standardize the information required under the EU MDD and regulations in other countries.
As medical devices and corresponding regulations developed more stringent regulations that defined their market access submissions, regulators found that this original harmonized format did not require sufficiently detailed technical information, nor did it provide enough structure. As a result, more recent regulations have replaced STED with expanded requirements. Note that some in the industry may refer to “STED” when discussing the newer requirements that have replaced it.
Is STED still valid?
Technical documentation formatted using STED may come close to meeting current requirements in some cases. However, many major markets have updated their regulations and requirements for technical documentation, or they have standardized on MDR. EU notified bodies expect MDR technical files, which may have specific requirements depending on the notified body that a manufacturer is using.
In addition to MDR in the EU, we have seen other countries over the past few years make changes to their regulatory systems and requirements, including:
- New regulations in China based on IMDRF in June, 2021 (Order #739)
- Emerging regulations in Canada and Brazil that are currently based on the IMDRF ToC
- New Regulations for Saudi Arabia that closely resemble EU MDR
- Massive regulatory restructuring in ASEAN market
What has replaced STED?
STED has been replaced by the IMDRF Table of Contents (ToC) submission dossier. This submission template has more defined requirements than STED and we are seeing countries update their regulations to adhere closely to the IMDRF ToC. There are a few additional benefits to the IMDRF ToC:
- Additional Flexibility - The IMDRF ToC has a specific numbering structure for technical requirements that allow authorities to “pick and choose” requirements based on submission type and risk classification.
- Efficiency – Countries that use the IMDRF ToC will have a matrix structure for their submissions to note what is required (R), Conditionally Required (CR), Not Required (NR) or optional (O). This can cut down on extraneous information that does not need to be in a submission. Canada already has draft guidance in place with their matrix submission style.
- Standardization – each country that follows the IMDRF ToC will number their submission document requirements with the same Table of Contents.
There are also other markets that are using alternative pathways to STED. The ASEAN market uses ASEAN CSDT (common submission dossier template), which is similar to the IMDRF ToC format, but uses different numbering. There are also two versions of the CSDT – one for standard medical devices and one for in vitro diagnostic devices.
Note that Singapore HSA has good information and is considered the “gold standard” for regulatory submission processes in the ASEAN market.
Expectations for future medical device submission requirements
We expect requirements to only get more complex and burdensome as countries move to further improve patient safety and address the needs of increasingly complex medical devices. A well-defined submission template strategy is critical to managing your device types. Within Rimsys, you can not only access standard IMDRF, NMPA, and other templates - you can design customized templates as needed for your holistic regulatory strategy.
Additional resources
Would you like to learn more about how Rimsys handles submission templates? Schedule a conversation with our experts now.

An overview of the UK Medicines and Healthcare Products Regulatory Agency (MHRA)
There’s no question that the medical device market is global, and the United Kingdom (England, Scotland, Wales, and Northern Ireland) is one of the world’s most viable and vital markets. It’s certainly one that you want your medical device in if you hope to make a global impact. The Medicines and Healthcare products Regulatory Agency (MHRA) is the gatekeeper of that market and one of the world’s most influential regulatory bodies.
Knowing who the MHRA is and understanding their role in ensuring that only safe, effective, high-quality medical devices enter the market is vital to your success in the UK. In this brief article, we’ll tell you more about who the MHRA is, their authority and responsibilities, and even some of the requirements you must meet to get your medical device into this market.
What is the MHRA?
The MHRA is an executive branch of the Department of Health and Social Care. It’s the UK’s equivalent of the US Food and Drug Administration (FDA), meaning that they set the quality and regulatory standards for medical devices in Great Britain.
Because the UK used to be part of the European Union, products required a CE marking to enter the UK market. Since Brexit, the MHRA has been the sole regulatory authority in Great Britain (England, Scotland, and Wales) and the gatekeeper to its robust medtech market.
What does the MHRA do?
As you know, medical devices must meet specific requirements before they can be sold in most markets around the world. Generally, the more developed the nation and its healthcare and medical device industries, the more complex its healthcare regulations are.
The MHRA is responsible for:
- Monitoring and regulating post-market surveillance of all medical devices currently on the market and creating regulations and requirements for medical devices entering the UK. They also enforce regulations, ensure medical devices meet the necessary safety, efficacy, and quality standards, and have the power to pull noncompliant products from the shelves.
- Making sure that supply chains for medical devices and the materials that comprise them are safe and secure. This includes everything from the facilities where products are made and stored, to their packaging and the systems and logistics applied in their transport.
- Educating the general public, healthcare professionals, and manufacturers about the risks and health benefits of medical devices.
- Engaging in harmonization efforts with other countries to develop standardized pathways to global markets. They influence international regulatory standards, best practices, and frameworks to support this effort.
How do you register a medical device with the MHRA?
Registering a medical device in the UK is different than in years past due to Brexit, which was the British exit from the European Union. Before Brexit, the UK adhered to the EU regulatory requirements as put forth in the EU MDD/IVDD, which Regulation EU 2017/745 (MDR) and Regulation EU 2017/746 (IVDR) eventually replaced. However, the MHRA will be instituting its new regulations currently set to be in force in July 2024.
One of the first steps of registering a product in the UK is getting the UK Conformity Assessment (UKCA) marking on your device and packaging. Manufacturers of Class I (lowest-risk classification) devices and general In Vitro diagnostic devices can self-certify against UKCA marking if these devices are non-measuring and non-sterile.
Class II and III devices must go through conformity assessment by a UK approved body. Approved bodies are the UK’s equivalent of Notified Bodies in the EU. These organizations have the authority to perform conformity assessments and apply UKCA markings on medical devices. UK approved bodies also perform post-market surveillance of devices currently on the market to ensure they’re safe and compliant for as long as they’re in use.
The process is a little different for device manufacturers outside of the UK who want to market their medical devices. Foreign manufacturers must designate a single person based in the UK to serve as their authorized representative (or UK Responsible Person). The UK Responsible Person acts as a liaison between the manufacturer and the relevant approved regulatory bodies, and handles the task of registering that company’s products with the MHRA.
The MHRA and Northern Ireland
When registering a device in Great Britain and Northern Ireland, you’ll notice that there are different procedures even though both were part of Brexit. According to the Northern Ireland Protocol (Northern Ireland’s response to Brexit), Northern Ireland applies Regulation EU 2017/745 (MDR) and Regulation EU 2017/746 (IVDR) to its own regulatory framework, whereas Great Britain has decided to implement its own regulations over the next couple of years.
For instance, as Northern Ireland still adheres closely to Regulation EU 2017/745 (MDR) and Regulation EU 2017/746 (IVDR), UK approved bodies cannot provide conformity assessments for them. In fact, if a manufacturer based in Great Britain wants to put a medical device on the market in Northern Ireland, they must designate an EU Authorized Representative to register the product for them.
Furthermore, an EU Notified Body must provide a conformity assessment according to Regulation EU 2017/745 (MDR) and Regulation EU 2017/746 (IVDR) for the device to receive UKNI marking (Northern Ireland’s conformity assessment mark). Likewise, Northern Ireland Authorized Representatives cannot represent Northern Irish or other foreign manufacturers in Great Britain, nor can Northern Ireland Notified Bodies provide UKCA marking for medical devices. In short, Northern Ireland has decided to continue to abide by EU medical device and in vitro diagnostics regulations as set forth by the European Medicines Agency, whereas Great Britain has not.
How to achieve compliance
The MHRA is firmly positioned as one of the foremost regulatory authorities in the world. They’re responsible for creating, implementing, and enforcing regulations for medical devices and IVDs in the UK while also providing research and education to promote the safety and efficacy of devices worldwide.
Adherence to UK regulations is essential to getting your medical device on that market and keeping it there. Medical devices entering the Great Britain market must adhere to the MDR/IVDR (until June 30, 2023) or UK MDR 2002, whereas Northern Ireland still abides by EU regulations.
Manufacturers based outside of Great Britain that want to put their devices on the market there must designate a UK Responsible Person (UKRP) to represent their interests and a UK-approved body to perform conformity assessments and apply UKCA marks. At the same time, Northern Ireland still adheres to EU regulations, requiring foreign manufacturers to utilize EU and NI responsible persons and notified bodies to assess medical devices, documentation, and manufacturing facilities while requiring the EU’s CE marking.
Bringing your device to market in the UK requires a dynamic regulatory strategy that enables you to optimize your projects and processes, ensuring your medical devices hit the mark for both the GB and NI markets. Also, it’s vital that you do your due diligence to ensure conformity with the regulations of both markets while also avoiding conflating their processes and regulatory requirements. Ultimately, getting your medical devices compliant with both markets could set your medtech company up to be a mainstay in the UK.

Introducing impact surveys
When we think of medtech regulatory affairs it’s easy to focus in on pre-market activities: the identification of market entrance requirements and the submission process to obtain market clearance for a new device. This is an important aspect of the work that RA teams do, but it’s definitely not all they do.
The reality is that regulatory work is never done because products are never done. Medtech companies are consistently making product updates, whether optimizing manufacturing or supply chains, adding accessories, working with new materials, or releasing software updates. This is normal, but in a highly-regulated industry, any of these changes can have an impact on a product’s license or market clearance status.
Impact assessments of new regulations, product or manufacturing changes, or standards updates are a core RA activity and one that we’ve focused on automating within Rimsys. Our unique “product-centric” data structure allows registrations, submissions, standards, and technical files to be linked to individual products. This association means that any RA team member can instantly pull a list of products that may be impacted by a standards change, or, conversely, a list of registrations that may be impacted by a product change.
Now we’ve enhanced Rimsys’ impact assessment capabilities by allowing teams to survey registration owners or country managers and collect their individual feedback about the impact of pending changes.
Feedback is a critical element of impact assessments
Communication and feedback within a broader regulatory team is a critical component of any impact assessment. In larger organizations, different teams often have responsibility for different regions, whether those are dedicated RA teams, consultants, or in-country representatives. A product or manufacturing change can impact any number of country registrations in different ways, so to properly assess the regulatory workload needed to process the change, teams need to gather and document input across the extended RA team.
Traditionally this activity has involved a flurry of emails, some shared spreadsheets, and no clear tracking or management, making it time-consuming and difficult to effectively collect this information.The new impact survey feature from Rimsys automates this task and centrally collects all of the necessary feedback within a consolidated project plan.
How it works
Impact surveys are included in the projects module in Rimsys. Now, when you start a new project request you can automatically send a survey to all of the owners for registrations that are associated with the project. Owners are notified to log into Rimsys, review the product details and any linked documentation, and fill out a short form to document whether they think their particular registration will be impacted by the proposed project, the remediation required (registration update, audit, etc.), and the expected time required.

Registrations where the owner indicates an impact are automatically flagged, and a progress bar provides an at-a-glance view of the survey status (completed responses, pending responses, % of registrations impacted). When the project request is approved, all impacted registrations and timeline are carried over to the active project plan.
Automated impact assessments deliver more than efficiency
The new survey feature is another key piece in our goal to streamline and automate as many regulatory activities as possible. Centralizing the surveys within the Rimsys platform ensures that everybody has access to the information they need to assess the impact of proposed changes on specific markets and registrations. It allows surveys to be completed more quickly and ensures that all of the potential impacts are incorporated into a project plan.
This allows RA teams to work more quickly, but more importantly, it ensures that all potential impacts are properly identified, preventing project delays and eliminating noncompliance risks. If a product design change unexpectedly invalidates a license in a particular country, companies may have no choice but to withdraw that product until it can be recertified. Regulatory automation isn’t just about increasing efficiency, it can also have a significant revenue impact.
Want to learn more about automated impact assessments in Rimsys? Contact us today for a custom demo.

Medical Devices: Comparing standards, regulations, directives, guidance, and laws
The energy sector, the financial sector, and the healthcare sector are some of the most heavily regulated sectors out there due to the possibility of significant risk to consumers in those industries. In particular, the healthcare sector is regulated to ensure that only the highest quality care is provided to patients and that medical devices are optimized for safety and efficacy.
In the world of Regulatory Affairs, words such as “standards” and “regulations” are used frequently. While they can be rather similar, they do have different meanings in different situations. Let’s explore their definitions and meanings when being used by medical device regulatory affairs professionals.
In general, legislative bodies pass laws, government agencies develop regulations to implement the laws, and industry groups and organizations create and approve standards.
Medical Device Standards
Standards refer to industry standards that device manufacturers use to design, develop, and manufacture safe medical devices. Standards help to demonstrate safety, manage risk, and to achieve regulatory compliance. Harmonized standards are used, when possible, to make working across borders easier.
Example: ISO, IEC, and UL are all examples of industry standard organizations that develop standards to help guide manufacturers on safe design, development, and manufacturing of quality products.
Standards are:
- Technical documents
- Driven by the need for a consensus
- Crafted by experts
- Approved by peers within the industry
Medical Device Laws
Laws are created by the government, as are regulations, but the two are different. Regulations are the practices which need to be followed to ensure that the law are followed.
Example: Criminal laws, civil laws, federal laws, international laws, etc.
Laws are:
- Rules created by the government
- Designed to regulate commercial and business transactions
- Legal rules that apply to all members of society and/or institute
- Not changed frequently
Medical Device Regulations
Regulations are the process of monitoring and enforcing established government rules and laws.
Example: The EU implemented the Medical Device Regulation (MDR) Regulation EU 2017/745 for all its member states. This regulates the clinical investigation and sale of medical devices for human use. If you want to sell a medical device in the EU, it must be designed, developed, and manufactured according to this regulation.
Regulations:
- Define processes for the monitoring and enforcing the laws
- Provide a consistent method to ensure laws are followed
- Are known to change often and without notice
Medical Device Directives
In Europe, Directives are legal acts of the European Union. Directives comply with the EU's desire for subsidiarity and acknowledges that different member states have different legal systems, allowing each member state the leeway to choose its own statutory wording.
Directives:
- Are legal acts set up by the European Parliament and Council .
- Require member states to uphold the acts without dictating specific processes.
- Allow member state to have flexibility as to how the rules are to be adopted.
Medical Device Guidance
Guidance documents are designed by federal and/or regulatory agencies, such as the FDA and European Union, and are meant to help further explain or provide clarity on existing rules.
Example: The FDA provides many guidance documents to help medical device manufacturers better understand the rules and regulations governing the safe design, development, and manufacturing of medical devices.
Guidance documents are:
- Designed by federal and regulatory agencies
- Intended to help people better understand legal rights and obligations
- Not designed to be enforceable under law
Medical Device Policies
A policy defines how an institution should execute a regulation. While it’s not against the law to not follow policy, failing to follow the policy can result in situations that cause an organization to operate outside of the law. The government creates regulatory policies to ensure that industries operate in a sustainable manner and that any risks are minimized (i.e., foreign policy, economic policy, ethics policy, environmental policy, etc.).
A Policy is:
- How an institution interprets and implements regulations.
- Is meant to execute a regulation, depending on an institution’s size, complexity, location, and other factors.
- Helpful in providing people with guidelines for making day-to-day decisions.
As you can see, there are many different rules, regulations, etc. that need to be considered and followed, and they can sometimes be intertwined. When developing and selling medical device equipment, it’s very important for regulatory affairs teams to understand how each needs to be followed. You also need to be aware of the constant changes, especially when doing business in more than one country. A regulatory information management system is a great place to start to ensure the security of your products – no matter where they are being distributed and sold.

EU MDR transitional period to be extended
The Council of the European Commission has concluded their December 9th meeting meant to address member states’ concerns over the challenges and issues in meeting current MDR deadlines. MDD certificates for medical devices will continue to be accepted for an additional three to four years beyond current MDR deadlines, with limited exceptions.
While not all details are available, it is believed that the following changes will be adopted:
- An extension of the transitional period, allowing medical devices to continue to be marketed under MDD certifications through 2027 for class IIb and class III devices, 2028 for class IIa and class I devices that require an external conformity assessment, and 2028 for class 1 devices that are sterile or have a measuring function.
- An extension of the validity of certificates issues under the MDD.
- Some restrictions will be put in place under the new extensions. Devices not eligible for extended deadlines will include those devices presenting an unacceptable risk, those that have undergone significant changes since being certified, and devices for which the manufacturers are already in the process of obtaining certification under the MDR.
- The removal of the existing “sell off” provision.
It is expected that the MDCG will release a guidance to address bridging the gap for expiring MDD certificates within the coming days and that the full legislative proposal will be introduced in January, 2023.
Stay tuned for additional information as we learn exactly how this will be implemented and what restrictions will be in place.
Additional articles and information:
- MDCG 2022-18: MDCG Position Paper on the application of Article 97 MDR to legacy devices for which the MDD or AIMDD certificate expires before the issuance of a MDR certificate
- New extension to implement MDR (MDlaw.eu)
- Summary of the EU Commission Meeting – including video (Easy Medical Device LinkedIn post)
- Jan 6 update - EC adopts proposal
- 6 reasons medtech companies shouldn't delay MDR certification

Making the case for a RIM system
Regulatory Information Management (RIM) systems are becoming more prevalent in medical technology companies of all sizes. Yet many regulatory teams still rely on spreadsheets and software designed for other purposes, such as quality systems or pharmaceutical regulatory applications. When your team is ready for a medical device RIM system, what information and arguments can you use to obtain the budget and executive buy-in you will need?
In this article, we discuss the benefits of a RIM system that can be used in calculating and estimating ROI, along with examples of results achieved by Rimsys customers.
Improved efficiency
Arguably the greatest benefit to implementing a RIM system is the increased process efficiencies it brings, but this benefit is often the most difficult to quantify. It is not difficult to imagine that moving from spreadsheets and manual processes to a dedicated regulatory information management system will improve efficiency, but how do you measure this?
- Eliminate “non-value add” work
Identify the processes on which your RA team spends the most “non-value add” time. How much time does it take for them to determine all of the countries in which a product is approved for sale? What registrations are expiring this year? What GSPRs need to be updated because a standard has changed? For many medical device manufacturers, these processes take hours, days, or even weeks, of combing through multiple data sources and verifying information. A properly implemented RIM system can be expected to provide this type of information in minutes. - Improve communication between departments
Consider how your systems and departments communicate with each other. When the product team makes a change, how quickly and seamlessly are the quality and regulatory teams notified? Do they always have the time they need to react to such changes? If the regulatory team identifies a new requirement that the quality and product teams need to be aware of - how seamlessly is that handled? A RIM system can not only identify items that need to be communicated to other teams, but can also be integrated with PLM, eQMS, and ERP systems to automate such communication. One good example of this is Rimsys’s ability to share a product’s selling status with the manufacturer’s ERP system. This ensures that a product is never sold into a market where it has not been approved. - Enforce company processes and workflows
A RIM system can help enforce your processes and ensure proper communication by managing approvals and other tasks within the system. By automating communications around process tasks, teams do not need to rely on individual emails (or remember to send those emails). RA teams don’t need to hunt through email history to confirm that they haven’t missed anything, and processes, approvals, and actions are recorded in a secure and compliant system.
Reduce the impact of RA staff turnover
A strong RIM system not only helps to reduce the risk and cost associated with staff turnover, but can also help reduce turnover in the first place! When RA staff turns over, or a new member joins the team, a RIM system will provide:
- Clear and defined processes that are standardized and built into the system.
- A central repository of product registration information, submission records, and more.
- Immediate availability of current and historical records when dealing with regulatory agencies and notified bodies.
A RIM system also speeds up the onboarding process new RA team members, which can otherwise take 6 months or more for employees to get fully up to speed on the product portfolio, in-flight and upcoming projects, and previous interactions with health authorities.
Providing your existing RA team with a well-implemented RIM system reduces the time they spend searching for information, allowing them to spend more time doing what they do best—implementing regulatory strategies and managing the regulatory affairs of the company. Your RA team will be more productive, feel more empowered, and be more likely to say in their role.
Minimize compliance risks
Medtech regulatory teams need to ensure that they are staying current with ever-changing global regulations, guidance documents, and standards. Each change needs to be evaluated for its impact on items such as existing GSPRs and pending compliance deadlines (think of the changing UDI labeling and database deadlines in many countries). RA teams are also responsible for ensuring that required reporting and submission deadlines are met for every product in every country in which they are sold.
RA teams that rely on manual processes and spreadsheets are opening their companies to a higher level of compliance risk than those using holistic RIM systems. RIM systems can automate many of the processes required to ensure regulatory compliance, including:
- Identification of GSPRs affected by a standards change.
- Notifications of pending license expirations and regulatory deadlines.
- Approval and notification tasks.
Without a central regulatory system and automated processes, required regulatory actions may be missed resulting in expired registrations that require products to be pulled from the market or audit findings resulting from information being incomplete or unavailable.
In addition, RIM systems like Rimsys are designed to be verified under 21 CFR part 11 requirements and provide quick access to data required during an audit or by a notified body or regulatory agency.
Reduced costs
Wasted time
Many of the RIM advantages discussed above also lead directly to cost savings. When making the case for a RIM system in your organization, use as much specific data as possible - including average RA salary and time-savings estimates based on your team and processes. In general, though, consider that:
- The average RA professional wastes 30-50% of their time looking for information that could be easily retrieved with a RIM system.
- The average salary of an RA professional is $97,000.
- Approximately $30-$49k of each employee's salary is wasted due to inefficient processes.
In addition, a RIM system may allow you to reduce the cost of outside consultants and contracted regulatory work. Medtech regulatory consultants can charge between $150 and $300 an hour - resulting in consultant fees in the millions of dollars for many medical device manufactuers. One Rimsys customer was able to eliminate 15 consultants at the time they implemented the Rimsys RIM solution.
Cost of non-compliance
If your organization is found to be out of compliance by any regulatory agency, the cost can be extremely high. Not only must you put time and effort into becoming compliant, but you may likely face fees, penalties, higher consultant fees, and other direct costs. If a product needs to be removed from a market, and then re-approved, the costs can be significant. The largest concern for most companies, however, may be the costs associated with a well-publicized non-compliance issue (often following an adverse event or major quality issue). While difficult to quantify, if your company has faced major recalls or other public issues, use the actual lost revenue and increased cost numbers as available.
According to a McKinsey report, the average share value of a company experiencing a major quality event drops by 16.8%. The same report lists the average cost of a recall in companies surveyed at $2 million, a warning letter at $1 million, and a consent decree at $400 million (this last number is one consent decree at a single company).
Increased revenue
We believe that regulatory teams do not get enough credit for driving revenue within their organizations. A well-run regulatory team with the right tools drives:
- Increased speed to market: Regulatory teams using RIM systems complete new product submissions and registrations renewals in much less time than those without dedicated regulatory software. This means more products getting to market more quickly. Consider estimating how many weeks/months you can reduce product submission activities by and estimate additional revenue based on expected product releases in the coming year.
- Less revenue at risk from compliance issues: The potential for lost revenue can also be reduced by improving regulatory processes through a RIM system. If a product needs to be pulled from a market or experiences a serious and public regulatory event, how much revenue will your company lose in that market during the months or years it will take to recover? Medical device manufacturers reduce this risk by implementing strong regulatory systems that ensure registration renewals, ongoing reporting requirements, and updated requirements are visible and well-managed.
Real-world examples from Rimsys customers
- A leading In-Vitro diagnostic manufacturer reduced the time it took to update the 1400 GSPRs they were managing when a single standard changed by from 360 person-hours (3 regulatory professionals x 3 weeks) to 30 minutes. The time to create a GSPR table was reduced by 50% and required maintenance was reduced by 99%. (read the full case study)
- One medical device company had no communication between their PLM, eQMS, and ERP systems - causing delays in getting products registered and into new markets. They implemented Rimsys (replacing existing spreadsheets) and streamlined their product authorization process - reducing workload by 88%. It now takes just a few minutes to determine where a product is sold, versus the hours it took previously. (read the full case study here)
- BISCO, a leading global manufacturer of dental adhesives and cement, has a well-organized product registration process, but the information was difficult to share and search. Maintaining essential principle tables was also a growing concern. According to Ryan Hobson, BISCO's Global RA Manager, Rimsys allowed them to take “a process that could take a week or a week-and-a-half all told, and shortened it to a matter of minutes.” (read the full case study here)

Looking for information and data you can use to make the case for budget or leadership buy-in for a regulatory information management project? Download our RIM ROI infographic for a quick reference of all of the potential cost savings and revenue growth that can be realized with a RIM system.
